


A Patient, a Missed Signal and a Bigger System Problem
Dental teams may be well placed to identify wider health risks, but screening alone is not enough. The real challenge is creating clear pathways so clinically useful information can move between professionals and lead to meaningful action.
A patient I had been seeing regularly suffered an aneurysm associated with previously undiagnosed high blood pressure.
It stayed with me.
Not because I thought dentistry should somehow have prevented what happened, but because it raised a bigger question:
If earlier signs had been picked up in another part of the healthcare system, would that information have had anywhere useful to go?
That question led me to think more closely about the role dental teams could play in wider health screening — and, more importantly, what needs to happen after a risk is identified.
Could dentistry play a wider role?
Dental professionals see many patients regularly, sometimes more consistently than other parts of the healthcare system.
We already take medical histories, assess general health risks and consider medical conditions when planning safe dental care.
That makes the dental setting an interesting place for wider health screening.
Blood pressure is a good example.
In England, blood-pressure screening is not yet a universal part of routine dental care, although NHS England has been trialling blood-pressure checks in dental and optometry settings as a way of identifying people at risk of cardiovascular disease.
In the United States, blood-pressure measurement is already recognised by the American Dental Association as an important screening vital sign within dental care.
So the idea itself is not particularly radical.
The more important question is what happens next.
Detection is only the beginning
Imagine a dental professional identifies a significantly raised blood-pressure reading.
The patient is advised to speak to their GP.
Then what?
In many situations, the patient becomes responsible for carrying that information from one part of the healthcare system to another.
Some will act immediately.
Others may delay.
Some may misunderstand the significance of what they have been told.
And some information may simply never reach the professional who needs to see it.
That is where the issue becomes much bigger than screening.
The problem is not simply whether we collect the data
Adding another check to a dental appointment has consequences.
It takes time.
It affects workflow.
It creates additional responsibility.
And clinicians will quite reasonably ask:
What happens to this information once I have collected it?
If identifying a raised blood-pressure reading leads to an effective referral pathway, appropriate follow-up and earlier intervention, the value is clear.
But if the process ends with:
“You should probably speak to your GP about that.”
then much of the burden still sits with the patient.
We may have generated useful information without creating an effective route for that information to influence care.
When information cannot travel
This is a wider healthcare communication problem.
Healthcare systems generate enormous amounts of information.
But information only becomes useful when it reaches the right person, at the right time, in a form that supports action.
A dental team can identify a potential risk.
A GP can manage hypertension.
A patient can act on advice.
But if those parts of the system are not connected, each person is working with only part of the picture.
That creates a communication and interoperability gap.
A workflow problem as much as a clinical one
It is tempting to frame questions like blood-pressure screening as:
Should dental teams do this?
But implementation requires a broader set of questions:
Who is responsible for acting on an abnormal result?
How should that information be communicated?
Is there a clear referral pathway?
Does the receiving professional know why the patient has been referred?
Can the dental team see whether follow-up happened?
How much additional work does the process create?
Where does responsibility begin and end?
Without those answers, adding more screening can create more data without necessarily improving the pathway around it.
We may have a connection problem
The real opportunity is not simply to collect more health information in dental settings.
It is to create better connections between the information already being collected across healthcare.
That means thinking about communication alongside technology.
How does information move?
Who needs it?
What context travels with it?
What happens next?
And how do we make sure the patient does not become the only bridge between two disconnected systems?
Those questions matter whether we are talking about blood pressure, diabetes risk, medications, oral cancer, or wider links between oral and systemic health.
Better detection needs better pathways
Screening has value when it changes what happens next.
That requires more than recognising a signal.
It requires clear communication, defined responsibility and systems that allow useful information to move between professionals.
Otherwise, we risk identifying more potential problems without building the pathways needed to respond to them.
The challenge is not simply detecting more.
It is making sure what we detect can actually lead somewhere.
This is the kind of systems and communication gap I help oral health and digital health teams explore — where useful information exists, but the pathway around it makes it harder to translate that information into real-world action.
Why health advice doesn’t stick — and what oral health can teach us about making habits easier
Health advice doesn’t fail because people don’t care. It fails because real life creates friction. Here’s what oral health can teach us about designing habits that actually stick — with clearer priorities, better prompts, and more supportive systems.
January is peak “new habits” season.
And yet, every year, many of those habits quietly fade — not because people don’t care, but because real life gets in the way.
In oral health, I see this all the time.
I’m Colette — a UK-based dental clinician and medical writer — and I spend a lot of time thinking about the overlap between oral health, prevention, and the systems (and tech) that make healthy habits easier to stick to.
Because advice can be clinically spot-on… and still not stick.
In clinic, it’s often clear that knowledge isn’t the missing piece. Many patients already know the basics: brush twice a day, clean between teeth, watch the sugar.
And yet, a patient said to me recently:
“I know what I’m meant to do… I just don’t manage it.”
That gap — between knowing and doing — is where prevention often breaks down.
And it’s why motivation alone is rarely the answer.
Why health advice doesn’t stick (even when it’s correct)
Most oral health (and general health) advice is well-intentioned and evidence-based.
But behaviour doesn’t happen in ideal conditions. It happens on busy mornings, late nights, shift patterns, school runs, sensory overload days, anxious days, and the “I’ve got nothing left in the tank” days.
So when habits slip, it’s rarely because someone doesn’t care.
More often, it’s because the habit sits behind too much friction.
Common reasons health habits fail (the friction points)
Too much complexity
Too many products, too many claims, too many “rules”. When people feel confused, they often do nothing.
No clear priority
If everything sounds equally important, it’s hard to know what matters today.
Timing
Advice is often given at a moment when people can’t act. The moment passes, and life takes over.
Shame and self-judgement
If someone feels they’ve already “failed”, they avoid the topic altogether. Shame doesn’t build habits — it blocks them.
Life factors that don’t get acknowledged
Neurodivergence, anxiety, depression, medication-related dry mouth, chronic illness, caring responsibilities, cost. These aren’t edge cases — they’re real life.
This is why I keep coming back to a simple idea:
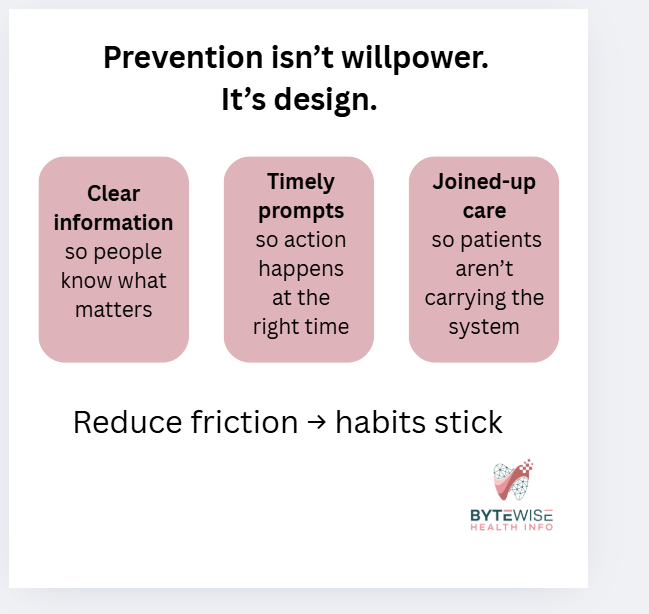
Prevention is easier when the system is designed to support it — not with more pressure, but with better support.
Knowing vs doing: where prevention really lives
Most prevention challenges sit in the gap between:
Capability — Do I know how? Do I have the tools?
Opportunity — Is my environment set up to help me?
Motivation — Do I want to do this, and does it feel worth it?
We often focus heavily on motivation: try harder, be consistent.
But opportunity is frequently the missing piece — the prompts, routines, environment, and joined-up care that make follow-through more likely.
This is also where digital tools can help — including reminders, smart prompts, and in some cases wearables — as long as they’re designed around real human behaviour, not perfect routines.
What better systems (and tech) could do
This isn’t about fancy gadgets or downloading yet another app that gets abandoned by Thursday.
It’s about reducing friction and making prevention easier to repeat.
1. Personalised prevention, not one-size-fits-all
Oral health advice is often generic — but people aren’t.
Someone with dry mouth, braces, diabetes risk, previous gum disease, or high sugar exposure needs different support from someone who’s low risk.
Better systems could translate risk into clear, usable guidance like:
“Here are your top two priorities this month.”
“Here’s the one habit that will give you the biggest win.”
“Here’s what to focus on until your next visit.”
Clarity reduces overwhelm.
2. Prompts at the right moment (not random reminders)
Most reminders fail because they arrive when you can’t act.
More effective prompts show up at the point of decision — when a routine is already happening.
Even low-tech prompts work well:
linking interdental cleaning to an existing habit
keeping brushes or floss where you actually sit
a simple routine card on the bathroom mirror
recall messages sent during opening hours, when booking is easy
Tech can help with timing — but the goal is simple: make the next right action easier.
3. Joined-up records that support joined-up care
Oral health is linked to systemic health, medication, pregnancy, and chronic conditions — yet records are often siloed. This is something I explore further in my white paper on integrating dental and medical health records.
When data isn’t joined up, we rely on:
patients repeating their story
memory (not a safe clinical tool)
missed prevention opportunities
Better integration could flag:
diabetes risk and gum inflammation
medication-related dry mouth
anticoagulants and dental planning
osteoporosis medications
pregnancy-related inflammatory windows
This isn’t about “more data”.
It’s about the system doing some of the heavy lifting — so patients don’t have to.
4. Prevention that continues between appointments
Most people see a dental professional occasionally — but habits are daily.
Systems and tech could help bridge that gap with:
simple check-ins
consistent, non-judgemental encouragement
short, personalised “next step” nudges
easy access to the right education at the right time
Prevention works best when it feels supported, not like a once-a-year reset.
Three tiny friction-reducers to try this week
You don’t need a personality transplant. You need a simpler setup.
1. Put tools where the habit actually happens
Out of sight = out of routine. Move tools to where you intend to use them and leave them on show.
2. Attach the habit to something you already do
Borrow an existing routine so you don’t rely on memory.
3. Shrink the task
A “minimum version” still counts. Consistency beats perfection.
A quick note on shame
If you’ve ever felt embarrassed about your oral health routine, you’re not alone.
But shame doesn’t create good habits.
It creates avoidance.
Better systems support people — they don’t judge them.
Where I’m going with this in 2026
This year I’m leaning further into the systems side of prevention.
Not just what we tell people to do — but what actually helps people do it, consistently, in real life.
That includes:
clearer risk communication
better-timed prompts
joined-up records
and tech that supports habits without adding guilt
I’m also starting a behaviour change course to strengthen this side of my work — so my content is not only clinically accurate, but genuinely usable.
One last question
What’s the biggest thing that gets in the way of oral health habits sticking — for you, or for your patients?
Forgetfulness?
Time?
Anxiety or sensory issues?
Cost or access?
Medication or health factors?
Or just… life?
These real-world barriers are where better prevention design starts.