


When Patients Understand the Advice — But Still Don’t Act on It
Patients can understand oral health advice and still struggle to act on it. This article explores the practical, physical and personal barriers that can sit between understanding and behaviour.
Sometimes patients understand exactly what we’re telling them about their oral health.
They know why interdental cleaning matters. They understand why ongoing periodontal care has been recommended. They know smoking affects their oral health.
And still, nothing much changes.
The natural reaction is often to explain it again. Maybe the information needs to be clearer. Maybe we need a better leaflet, another conversation or a different way of getting the message across.
Sometimes that is exactly what’s needed.
But sometimes understanding isn’t the problem at all.
Good dental patient education can help people understand their oral health, make informed decisions and know what they can do next. But knowing what to do is only one part of what influences whether somebody actually does it.
If a patient already understands the recommendation, the more useful question may be:
What is actually getting in the way?
The same behaviour can have very different causes
This is something I see regularly in clinical practice.
Two patients may both leave an appointment without using the interdental brushes that have been recommended.
From the outside, the behaviour looks exactly the same.
But one may have arthritis in their hands and fingers. They want to maintain good oral hygiene and understand perfectly well why interdental cleaning matters, but physically they just cannot manage the brushes easily.
Another patient may be perfectly capable of using them but feel uncomfortable with the amount of plastic waste involved in using disposable products every day.
The behaviour looks the same. The barrier isn’t.
And that matters, because neither problem is likely to be solved by simply explaining the benefits of interdental cleaning again.
One person may need an alternative that is physically easier to use. The other may need an option that sits more comfortably with their environmental values.
Evidence suggests that personalised oral-health education can improve knowledge, confidence and oral-health behaviours.
The education has not necessarily failed. It may already have done its job.
Knowing what to do and being able to do it are different things
It is easy to treat a lack of action as a lack of understanding.
But sometimes people know exactly what they should be doing and simply cannot do it in the way we have suggested.
The patient with arthritis is a good example. More information will not improve the dexterity in their fingers.
The same can apply to people who find certain tastes, textures or sensations difficult to tolerate. An oral-health routine that looks simple on paper may be much harder for somebody with sensory sensitivities.
At that point, the question changes.
It is no longer simply, “Have we explained this clearly?”
It becomes, “Is what we are asking actually manageable for this person?”
That distinction is important for anyone designing patient information, education or support.
Sometimes everyday life is the barrier
Even when somebody understands the recommendation and feels motivated to follow it, their circumstances may make it difficult.
I have patients who travel several hours to attend appointments, and occasionally even fly in. They may understand that more frequent hygiene visits would be beneficial and genuinely want to attend more often, but the travel makes that unrealistic.
That isn’t an education problem.
It’s an access problem.
Cost can create a similar gap between intention and action. Some patients start really well with interdental brushes or other aids, but when they are getting through them regularly, the ongoing expense begins to add up. On a tight household budget, that can eventually become difficult to sustain.
Other health concerns may understandably take priority too. Oral health is important, but it exists alongside physical health, mental health, family responsibilities, work and everything else happening in somebody’s life.
More information cannot remove all of those competing pressures.
And sometimes it comes down to what matters to the person
There is another reason people may understand advice without following it: it conflicts with something else they value.
The environmental example is a good one.
If somebody is trying hard to reduce plastic waste, recommending a product they view as disposable and environmentally unfriendly may create a genuine conflict.
Repeating the clinical benefits more loudly does not make that concern disappear.
That does not mean the person is disengaged or does not care about their oral health. They may simply be weighing the recommendation against another value that matters to them.
For brands and organisations developing oral-health products or patient education, that is worth understanding.
Sometimes the question is not “How do we explain the benefits better?”
It is “What is making this recommendation difficult to accept, use or sustain?”
If a patient already understands the recommendation, it is worth looking at what else might be influencing whether they are able to act on it.
More information is not always more support
Healthcare is very good at creating information.
If patients keep asking the same question, we create a leaflet. If engagement is poor, we write another explanation. If people are not following advice, we produce another resource.
And sometimes that is exactly the right response.
But education can solve an understanding problem. It cannot solve every barrier to action.
If the patient does not understand, improve the explanation.
If they understand but cannot physically do it, the answer may be adaptation.
If access or cost is the problem, more content is unlikely to remove it.
If the recommendation conflicts with their priorities or values, the useful work may begin with understanding those concerns.
The important part is working out which problem we are actually dealing with.
Start with the behaviour, not the leaflet
For dental organisations, oral-health brands and education teams, it can be tempting to begin with the content.
What should the leaflet say? What should go on the webpage? Do we need a video? Should we explain the benefits more clearly?
There is a useful question to ask before any of those:
What needs to be different after somebody receives this information?
Then look at what might stand between the information and the behaviour you hope to support.
Do they understand it? Can they actually do it? Does their situation make it possible? Does it fit with what matters to them?
Those questions can lead to very different solutions.
Sometimes the answer will be better patient education.
Sometimes it will be a different product, a practical adaptation, better access, additional support or simply a more realistic expectation of what somebody can manage.
And sometimes the most useful discovery is that information was never the missing piece.
Better patient education starts with understanding what problem the education is actually being asked to solve.
Related reading
Sometimes understanding is the missing piece. This is explored further in the insight ‘Your Audience Doesn’t Know What You Know’ which explains what happens when expert knowledge creates gaps between what organisations communicate and what their audiences understand.
Free resource
Not sure whether you’re dealing with a content, training or workflow problem?
My free ‘what’s actually going wrong?’ PDF guide offers a simple way to start working out where the problem actually sits.

Content problem, training problem or workflow problem? How to work out what’s actually going wrong
When uptake is low, engagement is poor or the same questions keep coming back, creating more content can feel like the obvious answer. But the same symptom can have very different causes. Here’s how to work out what is actually going wrong before you add more content to the pile.
There are plenty of people who will happily create more content for you.
Especially when creating content is what they are being paid to do.
But before another explainer, FAQ, training module or campaign gets added to the pile, there is a more useful question to ask:
Does this content actually need creating?
That can be surprisingly difficult to answer when you work inside an organisation or industry.
You already know too much.
You know the terminology, the process, the product, the background and the reason something exists. You cannot completely remove that knowledge and experience the communication in the same way someone seeing it for the first time would.
That is often where clarity gets lost.
The problem is not always that organisations lack content.
Sometimes they lack clarity about what problem the content is actually supposed to solve.
The same symptom can have very different causes
Imagine a healthcare organisation launches a new digital service and uptake is poor.
The first instinct might be to rewrite the patient information.
But what if patients understand the service perfectly well and staff simply do not remember to introduce it?
That starts to look more like a workflow or training problem.
What if staff explain it consistently, but patients abandon the sign-up process halfway through?
That points more towards user experience.
And what if the service itself works well, but the people most likely to benefit do not have reliable digital access?
That is an access problem.
Same symptom.
Very different cause.
This is why jumping straight to “we need better content” can be expensive, time-consuming and ineffective.
Is it actually a communication problem?
If people keep asking the same question despite already being given the information, that does not automatically mean they need more information.
It may mean the message is unclear, badly timed or simply not answering the question they actually have.
You might see patients or professionals misunderstanding what something is for, hesitating because they are unsure what happens next, or different teams describing the same product or service in completely different ways.
Sometimes the information is technically correct but still hard to make sense of.
In those situations, communication probably does need attention.
That might mean changing the language, reorganising the information, making the next step clearer or explaining the value of something in a way that feels relevant to the person receiving it.
But first, you need to know that understanding really is the problem.
Or is it a training problem?
Sometimes the patient-facing information is fine.
The problem sits with the people expected to explain or support it.
A team may understand the broad idea behind a new service or process but still feel unsure about how to talk about it in practice.
One person explains it one way. Another barely mentions it. Someone else avoids discussing it because they are worried they will be asked a question they cannot answer.
That can quickly create inconsistent communication.
In healthcare, I see this distinction matter a lot.
The training may have been delivered. The information may exist. Everyone may technically know what is supposed to happen.
But that does not necessarily mean they feel confident putting that knowledge into practice.
If the gap is between knowing and doing, another patient leaflet is unlikely to fix very much.
Could the workflow be the real problem?
You can explain a process perfectly and still get poor uptake if the process itself is a nuisance to follow.
People may understand exactly what they are supposed to do and even agree that it matters, but the way the process works makes it harder than it needs to be.
Perhaps a referral takes too many steps.
Maybe staff have to leave one system and log into another.
Responsibility may be unclear.
Or the new process simply does not fit naturally into an already busy clinical day.
This is where you start to see workarounds, forgotten tasks and good intentions disappearing as soon as things get busy.
If the workflow is making it harder for people to do what you need them to do, more communication may simply add another layer to the problem.
What if the system itself is hard to use?
This is where user experience, or UX, becomes important.
Take digital medical history forms.
Dental practices often ask patients to update their medical history online before an appointment. When the information comes back incomplete, it is easy to assume the patient has not read the instructions properly or has simply missed something.
But that is not always what is happening.
Sometimes the wording is unclear and the patient does not understand what information they are being asked to provide.
Sometimes the wording is perfectly reasonable, but the form itself is difficult to navigate. The patient may not know what to click, whether they have selected the right option, or whether the form has actually been submitted.
From the practice side, the symptom looks the same:
an incomplete medical history form.
But the cause could be very different.
One problem may need clearer communication.
The other may need a better user experience.
And in some cases, it may be a bit of both.
That is why it helps to look beyond whether someone completed the task and ask where they actually got stuck.
And sometimes it is an access problem
There is another possibility.
People may understand the message.
They may know what to do.
The process may be simple.
And they still cannot act.
Cost, time, language, transport, digital access or competing priorities can all create barriers that communication alone cannot remove.
That distinction matters.
Otherwise, organisations can end up trying to solve an access problem with more information.
Sometimes people are not failing to act because they do not understand.
They simply cannot easily do what is being asked of them.
Before you create more content, ask a different question
Instead of starting with:
What should we create?
Start with:
What is stopping the behaviour we want?
Then work backwards.
Do people understand what they are being asked to do?
Do they believe it is relevant to them?
Do staff know how to support it?
Does the workflow make it easy?
Is the system intuitive?
Can people realistically access what is being offered?
Those questions help separate the symptom from the cause.
And that matters because the wrong diagnosis usually leads to the wrong fix.
Sometimes the hardest part is being too close to the problem
This is where internal teams can struggle.
When you know a product, service or process inside out, it becomes difficult to see what someone else does not know.
You fill in gaps automatically.
You understand the terminology without thinking about it.
You know where to click, what happens next and what a sentence is trying to say, even when none of that is obvious to someone encountering it for the first time.
That does not mean the internal team has done anything wrong.
It simply means familiarity changes what you notice.
And sometimes that is exactly when an outside perspective becomes useful.
Not someone whose first instinct is to create more material, but someone who can look at what is already there and investigate what is actually not working.
Communication matters. But it cannot fix everything.
Better communication can solve a communication problem.
It cannot repair a workflow that makes things unnecessarily difficult.
It cannot replace training.
It cannot make an awkward system easy to use.
And it cannot remove an access barrier.
There is no shortage of content that can be created.
The more useful question is whether creating it will actually solve the problem.
If the answer is not obvious, that is often the point where a structured outside review can help bring some clarity.
Not sure what is actually getting in the way?
My Communication Clarity Audit is designed to help identify whether the problem sits with the communication itself, the training around it, the workflow, the user experience or something else.
Prefer to work through it yourself first?
I’ve also created a short diagnostic guide to help you work out where the problem may be sitting.

Why Good Health Advice Still Doesn’t Change What People Do
People can understand health advice perfectly well and still struggle to act on it. This article explores the gap between knowing and doing, and why timing, friction, confidence and real-life context matter.
In oral health, I see this all the time: people often know exactly what they’re supposed to do, but still struggle to do it consistently.
Most people do not need to be told that brushing twice a day is important.
They probably know they should clean between their teeth too.
They may already understand that frequent sugar exposure increases their risk of decay.
And yet, in clinic, I regularly hear some version of:
“I know what I’m supposed to do. I just don’t manage it.”
That sentence says a lot.
Because when people already understand the advice, giving them more information is unlikely to solve the problem.
The gap is somewhere between knowing and doing.
And that gap matters far beyond oral health.
Health brands, services and education providers can create clear, accurate, evidence-based information and still find that people do not act on it in the way they expected.
The problem is not always the information itself.
Sometimes the more useful question is:
What is getting in the way of someone using it?
Knowledge is only part of behaviour
Health communication often starts from a reasonable assumption:
If people understand what to do and why it matters, they will be more likely to do it.
Sometimes that is true.
But behaviour happens in real life.
On rushed mornings.
At the end of long working days.
Around children, caring responsibilities, financial pressures, health conditions and competing priorities.
Something can make perfect sense in an appointment, training session or product guide and still be difficult to carry into everyday life.
That is why repeating the same advice can sometimes have surprisingly little effect.
The person may already know it.
What they are missing is the ability, opportunity or confidence to turn that knowledge into action.
Friction changes behaviour
One of the things I notice frequently in oral health is how small amounts of friction can derail a good intention.
Interdental cleaning is a simple example.
Someone may genuinely want to do it.
But perhaps the brushes are kept in a cupboard downstairs.
Perhaps they are unsure which size to use.
Perhaps it takes longer than they expected.
Perhaps their gums bleed when they start, so they assume they are doing something wrong.
None of those problems is solved particularly well by telling them once more that interdental cleaning is important.
The useful question is:
What is making this behaviour harder than it needs to be?
That shift matters.
Instead of assuming the communication has failed because somebody did not listen, it looks at the conditions surrounding the behaviour.
[Insert infographic here]
Prevention isn’t willpower. It’s design.
Clear information so people know what matters
Timely prompts so action happens at the right time
Clear next steps so people know what to do next
Reduce friction → habits stick
Timing matters too
Sometimes good advice arrives before someone is ready to use it.
A patient may hear several pieces of information during an appointment but only remember the one that felt most relevant at the time.
A person may skim instructions when they first buy a health product, then realise two weeks later that they are unsure how often they should use it.
A clinician may complete training months before encountering the situation where that information becomes important.
The information was available.
It was understood at the time.
But the point of need came later.
This is why useful health communication often needs to do more than deliver information once.
It needs to consider when that information will become relevant again.
More information can sometimes create more friction
There is also a temptation in healthcare to respond to uncertainty by adding more.
Another leaflet.
Another webpage.
Another explainer.
Another list of instructions.
But more information is not automatically more useful.
If everything feels equally important, people are left to work out what deserves their attention first.
That can be particularly difficult when someone is already worried, overwhelmed or unfamiliar with the subject.
Often, the most useful communication is not the one that explains everything.
It is the one that makes the next useful action clear.
What should I focus on now?
What matters most?
What should I do if this happens?
When do I need help?
Clarity can reduce friction just as much as simplifying the physical process itself.
What people actually do gives you useful information
If health advice is not producing the behaviour expected, there is a lot to learn from what happens next.
Do people keep asking the same question?
Do they create their own workaround?
Do they start but stop after a few days?
Do they avoid one part of the process?
Do they understand the advice but struggle to fit it into their routine?
Those behaviours are not just failures to follow instructions.
They are clues.
They can point towards problems with timing, confidence, complexity, accessibility, perceived value or the environment in which the behaviour is supposed to happen.
And different barriers need different responses.
A knowledge gap might need better explanation.
A confidence gap might need reassurance or practice.
A complicated process might need simplifying.
A poorly timed message might need to reappear later.
More education is only useful when lack of education is actually the problem.
Good communication should make action easier
This is the part of health communication I find increasingly interesting.
Not simply:
Was the information accurate?
But:
What happened after somebody received it?
Did they understand it?
Could they remember it when they needed it?
Did they know what to do next?
Did the behaviour fit realistically into their life?
If not, where did things start to break down?
For health brands, services and clinical education teams, that distinction matters.
Because sometimes the communication has technically done its job.
The information exists.
The evidence is correct.
The explanation is clear.
But if people are still not able to act on it, the answer may not be another piece of content.
It may be worth looking more closely at what is happening between understanding the message and using it in real life.
That is often where the more useful problem sits.
If your organisation has already created the information but people still are not responding or acting as expected, my Communication Clarity Audit looks at where that gap may be — and what might need to change.

Why the Same Questions Keep Coming Back — and What Health Brands and Services Can Learn From Them
The same question keeps coming back, even though the information already exists. This article explores what repeated questions can reveal about timing, findability, language, consistency and the next step people actually need.
“We’ve already explained that.”
It is an understandable reaction when the same question keeps coming back.
The information is on the website.
It might also be in an FAQ, a leaflet, an onboarding email, a product guide or somewhere else in the customer or patient journey.
And yet people are still asking.
At that point, it is tempting to assume they simply have not read the information.
Sometimes that will be true.
But sometimes the repeated question is telling you something more useful.
Maybe the information is difficult to find.
Maybe it arrives at the wrong point.
Maybe the language makes sense internally but not to the person looking for an answer.
Maybe the information technically answers the question, but does not make the next step clear.
For health brands and services, those repeated questions are not just an inconvenience.
They can be clues.
Because information existing is not the same as information landing.
Repeated questions are useful communication data
If the same question appears again and again, it is worth paying attention to where it is coming from.
Customer support queries.
Search terms.
Online reviews.
Clinician feedback.
Comments on social media.
Questions asked during appointments.
Emails from users.
None of those sources will give you the whole picture on their own.
But together, they can start to show where people are getting stuck.
A health brand may know that a product page contains the answer.
A service may know that a patient information leaflet explains the process.
A digital health company may know that onboarding covers a particular feature.
But if people are still asking the same question, the useful thing to explore is not simply whether the information exists.
It is whether people can find it, understand it and use it when they actually need it.
Timing changes what people are ready to hear
Sometimes the information is perfectly clear.
It is just arriving at the wrong moment.
People do not absorb every piece of information they are given equally.
If something does not feel relevant yet, it is easy for it to pass by.
Then, a few days or weeks later, the same person reaches the point where the information suddenly matters and asks the question again.
That does not necessarily mean they ignored what they were told.
It may simply mean they were not ready to use it yet.
This happens all the time in healthcare.
A patient might be given advice before a procedure, then only think of the practical questions once they are at home recovering.
Someone buying a health product may skim the instructions, then only realise later that they are unsure how often to use it or whether it is suitable alongside something else.
A user may complete digital onboarding, then forget part of it because they have not yet needed that feature.
The information existed.
But the moment it became useful came later.
That is why communication should not only ask:
“Have we told people this?”
It should also ask:
“Will this information appear again when they are most likely to need it?”
People do not always look for information the way organisations expect
Information can be there and still be hard to find.
A brand might organise a website around product categories, clinical terminology or internal departments.
A patient or customer is more likely to be thinking:
Is this normal?
Can I use this every day?
What should I do next?
Is this suitable for me?
That difference matters.
If the information is filed under a heading people would never think to search for, they may never reach it.
The same thing happens with language.
A health service may use technically correct terminology that makes perfect sense internally, while the person looking for an answer is using completely different words.
Neither side is wrong.
They are just speaking from different starting points.
Good communication needs to bridge that gap.
That might mean using the language people actually use in search, FAQs and support queries.
It might mean restructuring information around questions rather than organisational categories.
Or it might simply mean making the most useful answer easier to spot.
Because if people cannot recognise that the information is for them, it does not really matter that it exists.
This shows up in dental patient communication too
I see this clinically quite often.
One example is Corsodyl 0.2% mouthwash.
The product information advises about a month of use for gingivitis and also warns that tooth and tongue discolouration can occur. Medicines.org.uk
Yet I regularly see people who have been using it as part of their everyday routine for months, sometimes much longer.
Often I notice the staining first and ask directly whether they are using Corsodyl.
The answer is usually yes.
When I explain that it is intended as a treatment mouthwash rather than something to use indefinitely, the response is often:
“Oh, I didn’t know.”
And when I mention staining, I sometimes hear the same thing again.
The information exists.
It is on the product information.
But that does not automatically mean it has landed in a way that changes what someone does.
That is the bit that interests me.
Because dental patient communication is not only about whether information is accurate or available.
It is also about whether people notice it, understand its relevance and act on it.
Mixed messages create more questions
Sometimes the problem is not that information is missing.
It is that people are hearing slightly different versions of it in different places.
The website says one thing.
The leaflet phrases it another way.
A clinician explains it differently again.
Customer support adds another interpretation.
None of those versions may be completely wrong.
But together, they can create uncertainty.
And uncertainty usually creates another question.
This is especially important when people are trying to understand something that already feels unfamiliar or slightly worrying.
They are often not looking for more information.
They are looking for reassurance that the information they have is consistent.
For health brands and services, that means it is worth checking whether the same message holds together across the different places people encounter it.
Not word for word.
But clearly enough that the person receiving it does not have to work out which version to trust.
Because when communication starts to contradict itself, even slightly, people notice.
Understanding the information is not always enough
Sometimes people understand the information perfectly well.
They just do not know what to do with it.
A product page may explain how something works.
A leaflet may describe what to expect.
An email may give all the background.
But if the next step is vague, people are still left with a question.
Do I need to do anything now?
Should I contact someone?
Is this something I need to worry about?
When should I use this?
What happens next?
This is where communication can feel complete from the organisation’s side but still feel unfinished to the person receiving it.
The facts are there.
The action is not.
For health brands and services, that means useful communication should not just explain.
It should also make the next step obvious.
Sometimes that next step is to use the product in a certain way.
Sometimes it is to wait.
Sometimes it is to contact a clinician or support team.
Sometimes it is simply to know that no action is needed.
But if that is not clear, people will often come back and ask.
And that repeated question may be less about missing information and more about missing direction.
Look for the pattern before you look for the solution
If the same question keeps appearing, the useful part is not just the question itself.
It is the pattern around it.
Does it always appear at the same point in the journey?
Is it linked to one particular product, page or message?
Are people using the same words when they ask?
Does the confusion appear after a particular appointment, email or onboarding step?
Are clinicians or support teams hearing the same thing repeatedly?
That starts to tell you where to look.
One isolated question may not mean much.
But repeated confusion around the same moment, message or decision can point towards a communication gap worth investigating.
Sometimes the answer will be to create something new.
But sometimes the more useful change is to adjust what already exists: its timing, wording, location or the action it asks people to take next.
Information being available is not the same as communication working
It is easy to measure communication by what has been created.
A webpage exists.
An FAQ has been written.
The onboarding email has been sent.
The leaflet has been approved.
But none of those things, on their own, tell you whether the information has actually landed.
That is why repeated questions are worth paying attention to.
They can show you where people are still uncertain, where information is arriving too early, where language is not matching the way people think, or where the next step is not clear enough.
Sometimes the answer is to create something new.
Sometimes it is to make what already exists easier to find, easier to understand or better timed.
And sometimes the most useful thing you can do is simply stop treating the repeated question as a nuisance and start treating it as a clue.

Why Dental Software Training Fails — and What Teams Need Beyond a Product Demo
Dental software training can look successful in the room and still fall apart in practice. This article explores why product demos are not enough, how confidence and real-world workflows affect use, and why the first step is understanding what is actually getting in the way.
A dental practice invests in new software and begins rolling it out across the team.
The team attends a training session, gets shown the main features and has a quick tour of how everything works.
At the time, it can all seem fairly straightforward.
Then the software goes live.
A few weeks later, people are still asking how to complete certain tasks. Some features are barely being touched. Team members start creating their own shortcuts. One person somehow becomes the unofficial software expert.
And the obvious conclusion is:
Maybe the team needs more training.
Sometimes they do.
But sometimes the problem is that the training showed people what the software could do without really preparing them for what they would need to do with it once normal working life kicked back in.
A product demo is not the same as learning how to use software at work
A product demonstration has an important job.
It shows people what the system can do, where the main features sit and how the software is supposed to work.
But that is not quite the same as preparing someone to use it in the middle of a normal dental day.
In a training session, nobody is running ten minutes late, answering the phone, trying to finish a patient record and being interrupted by someone asking a question at the same time.
In practice, that is exactly the environment the software has to work in.
There is a big difference between:
“Here is what this software can do.”
and:
“Here is what you need to do when this situation happens in your role.”
A receptionist, clinician and practice manager may all use the same system, but they are using it for different reasons and making different decisions along the way.
The software is the same.
The job it needs to do for each person is not.
Training works better when it starts with the job, not the menu
Software training often follows the structure of the product.
Here is the diary.
Here is the patient record.
Here is the reporting section.
Here is how to send a message.
That makes sense from the point of view of explaining the system.
But once people start using it for real, their questions are usually much more practical.
What do I do if the patient cancels after I have already started this process?
Where should I record this information?
Can I undo that without affecting something else?
Which part of this am I actually responsible for?
What happens if another team member has already done one of these steps?
That is why it helps to talk to the people who will actually be using the software before the training happens.
What do they already struggle with?
Where do their current processes get awkward?
What tends to go wrong?
What do they need the software to help them do?
Those conversations can shape the training around real situations, instead of just working through the software one feature at a time.
And even then, some questions will only appear later.
That is normal.
You do not always know what you need to ask until you are actually trying to do the job.
I know that from experience.
When I was a dental nurse back in the early 2000’s, we were still largely using paper clinical records, although software was starting to appear in some surgeries.
Then I went off to university for three years to train as a dental hygienist and therapist.
By the time I came back into general practice, dental software had moved on very quickly. Computers were suddenly in every surgery and I was simply expected to know how to use the systems.
I had missed that whole period of transition.
There had been no software training built into my degree, and the hospital environment I had trained in was still very different from general practice.
So I did what a lot of people do.
I taught myself.
I learned enough to get the job done, and over time I became comfortable using the systems I needed.
But even now, there are features I have never been properly shown, and probably functions I do not even know exist that would be useful to me.
That is the problem with assuming that because someone is managing, they have been properly trained.
Sometimes people are simply very good at finding a way through.
Confidence matters more than it looks
There is another side to this too.
I work with a very experienced dental nurse who is completely capable, clinically confident and very good at her job.
But put a new piece of software in front of her and her confidence suddenly drops.
She worries about clicking the wrong thing.
She worries about losing information.
She worries that something will go wrong and she will not know how to fix it.
There is nothing wrong with her ability to learn the software.
She just needs more reassurance, more repetition and a bit more time before she feels safe using it independently.
Someone else might fly through the same training in half the time.
That does not mean one person is capable and the other is not.
It means people come into training with different levels of confidence, experience and comfort with technology.
Good dental software training needs to leave room for that.
Otherwise the people who appear to be “slow to adopt” can easily get overlooked when what they really need is support that helps them build confidence.
Sometimes it is not a training problem at all
If people keep struggling with the same part of a system, the answer should not automatically be to explain it again.
Maybe the process itself is awkward.
Maybe the instructions are unclear.
Maybe something that looked simple in the demo actually takes too many steps when someone is trying to do it during a busy clinic.
Or maybe the software simply does not fit well with the way that particular team works.
From the outside, all of these things can look the same:
people are not using the system as expected.
But the reason matters.
More training will not fix a usability problem.
A clearer guide will not solve a badly designed workflow.
And another product demonstration will not help if people already understand what they are supposed to do but the process itself is getting in the way.
Before creating another webinar, tutorial or onboarding session, it is worth asking:
What is actually stopping people from doing what we expected them to do?
Is it knowledge?
Confidence?
Lack of context?
A workflow problem?
A usability problem?
The behaviour might look similar, but the solution will not be the same.
Good training prepares people for the job, not just the product
Dental software training should absolutely help people understand how the system works.
But the best training goes further than that.
It starts with the people who are going to use it.
It looks at the situations they actually deal with.
It gives people a chance to practise realistic tasks.
And it recognises that support is often still needed after the formal training has finished.
Because successful training is not really demonstrated by everyone attending a session.
It is demonstrated by what they can do afterwards.
And if people are still struggling, the answer may not be more content or another demonstration.
Sometimes the most useful thing you can do is work out exactly where the gap is first.

What Happens After the Training Ends?
Clinical training can be clear, relevant and well designed, yet still fail to change practice. The reason is often not the learning itself, but the workflow, responsibilities and systems surrounding it.
Why knowledge alone rarely changes clinical practice
I have completed plenty of continuing professional development activities that taught me something useful.
I have also completed plenty that changed absolutely nothing about what happened at work the following morning.
The certificate confirmed that I had completed the activity. The assessment showed that I could answer questions about the information.
But no one returned a month later to ask:
What actually changed?
And perhaps more importantly, had anything around me changed to support it?
Did I communicate differently?
Did the team update a process?
Did the learning influence a decision?
Or did it remain in my head until everyday clinical demands gradually pushed it aside?
Completion is not implementation
Clinical education is often measured by what was delivered and completed.
Attendance can be recorded. Assessments can be marked. Certificates can be issued.
These measures show that someone encountered, and perhaps understood, the information.
They do not tell us whether it changed practice.
Understanding is only one part of practice change.
Even when learning is clear and relevant, people may struggle to apply it if the systems, workflows or responsibilities around them do not support the intended action.
A clinician may recognise a risk but lack a clear escalation pathway.
A team may understand a new protocol but have no shared process for applying it.
Staff may be trained to use a digital tool but find that it adds extra steps to an already pressured workflow.
The education may be good.
The barrier may sit elsewhere.
You cannot train your way out of a workflow problem
Education is sometimes commissioned as the solution when the real barriers are limited time, unclear responsibilities, unsuitable technology, missing prompts or a process that has never been agreed across the team.
That does not make education unimportant.
It means education must be designed as part of a wider system.
While developing a whole-team oral cancer safety exercise, I realised that knowing the warning signs was only one part of the task.
The learning also needed to consider:
who might hear a concern first
what each person should do within their scope
how the concern should be recorded and escalated
who would ensure the next step happened
The same principle applies to medication safety, infection prevention, digital technology and new clinical pathways.
People need knowledge, but they also need the confidence, opportunity and practical support to use it.
Three questions to ask before designing clinical education
1. What should people understand?
Identify the essential knowledge, the audience’s starting point and any misunderstandings that could prevent the message from landing.
2. What should they do differently?
Define the intended action.
Should someone recognise a risk earlier?
Ask a different question?
Explain something more clearly?
Document information consistently?
Follow a new process?
If the desired change is unclear, education cannot be designed effectively around it.
3. What needs to change around them?
Consider whether the working environment supports the intended action.
Do people have enough time?
Are responsibilities clear?
Does the workflow make sense?
Are appropriate prompts, tools and escalation routes available?
If the system makes the intended behaviour difficult, education alone is unlikely to solve the problem.
When learning and workflow do not connect
When organisations mistake completion for implementation, they may believe a problem has been addressed while the underlying workflow remains unchanged.
This can result in:
inconsistent decisions and patient communication
knowledge remaining with individuals rather than reaching the wider team
uncertainty about responsibilities and escalation
new tools being abandoned or used inconsistently
the same risks continuing despite repeated training
Digital tools can reinforce learning by providing guidance and prompts at the point of need.
But they cannot repair an unclear pathway or undefined responsibility.
A prompt is only useful if the person receiving it understands why it matters, trusts it and knows what to do next.
Clinical education, technology and workflow must support the same intended behaviour.
When they operate as separate initiatives, the gaps between them are where implementation begins to fail.
Align learning, workflow and reinforcement
Effective clinical education aligns three things:
1. Learning
People understand the relevant information and why it matters.
2. Workflow
The intended action fits clearly into everyday practice, with defined responsibilities and processes.
3. Reinforcement
Prompts, digital tools, team discussion and follow-up help the new behaviour continue after the course has ended.
This means beginning with the real-world outcome and working backwards.
Success is not simply that people completed the education.
It is that they can apply it confidently, their team can support it consistently and the wider system makes the intended action possible.
That is the difference between delivering information and designing education for practice change.
So, what happens after your organisation issues the CPD certificate?
Does the learning end there?
Or can people apply it, teams support it and systems reinforce it?
I help oral health, digital health and clinical education teams identify why communication and learning are not translating into practice, and what needs to change to improve understanding, confidence and action.
Because good clinical education should not only demonstrate that learning happened.
It should make better practice more likely to happen next.

Your Audience Doesn’t Know What You Know
Accurate health information does not always lead to understanding or action. Sometimes the real problem is a hidden knowledge gap between what an organisation knows and what its audience needs to know.
Helping my son revise recently taught me something important about knowledge gaps.
The subject was maths. He could do the calculations, but some of the terminology meant very little to him. Words such as expand and factorise were stopping him from understanding what the questions were actually asking.
Once we explained those terms, everything changed.
His ability had not changed.
The missing knowledge had.
It got me thinking about how often the same thing happens in healthcare.
A product can be clinically sound. Training can have been delivered. The information can be completely accurate.
And yet:
clinicians still do not explain it confidently
patients still ask the same basic questions
teams communicate different messages
training is completed, but behaviour does not change
uptake is slower than expected
Sometimes the problem is not the product, the evidence or the audience.
Sometimes there is simply a gap in understanding.
When expertise creates a blind spot
The closer we are to a subject, the harder it becomes to remember what it felt like not to understand it.
Health and digital health organisations naturally become familiar with the language, evidence and logic surrounding their products or services. Over time, things that once needed explanation begin to feel obvious.
That familiarity can create a blind spot.
Organisations may start communicating from the point they have reached, rather than the point their audience is starting from.
A patient may receive accurate information without enough context to understand what it means for them.
A clinician may learn how to use a digital tool without feeling confident enough to explain it to a patient.
Training may cover the facts without helping someone apply them in practice.
The deeper risk is that organisations mistake exposure for understanding, and understanding for adoption.
Giving someone information does not mean they understand it.
And understanding something does not necessarily mean they can use it, explain it or act on it.
What looks like resistance may be a knowledge gap
When people fail to understand, trust or adopt something, it can be tempting to blame resistance.
Perhaps the patient is “not engaged”.
Perhaps the clinician is “reluctant to change”.
Perhaps the team is “not ready for innovation”.
But sometimes the audience is not resistant at all.
The explanation simply started in the wrong place.
My son was not incapable of doing the maths or unwilling to learn. He was missing the knowledge needed to interpret the question.
Once we identified that gap, his response changed.
The same principle applies to health communication.
Before assuming an audience is disengaged or resistant, it is worth asking whether they were given the right information, at the right level, in a form they could actually use.
Three questions before you communicate
I use three questions to test whether health information is genuinely usable.
1. What do they already know?
Do not assume the audience shares the organisation’s language, context or starting point.
What knowledge do patients, clinicians or other users genuinely bring to the conversation?
2. What are we assuming they already understand?
This is often where the real gap sits.
What feels obvious internally because the organisation works with the product, evidence or technology every day?
What knowledge might the audience be missing that prevents the rest of the information from making sense?
This could include what a product does, why it is being used, where it fits, its limitations or what its use means for the person on the receiving end.
3. What must they be able to do next?
After reading the content or completing the training, what should the audience actually be able to do?
Make a decision?
Change a behaviour?
Use the product?
Explain it confidently?
Recommend it appropriately?
Ask informed questions?
If they cannot do the thing the communication was meant to support, the information may have informed them without preparing them to act.
Knowing how to use it is not enough
I experienced this gap myself after receiving training on an intraoral scanner.
I could use the scanner competently. I understood how to capture the images and incorporate it into an appointment.
But if a patient had asked where their data would be stored, who could access it or what would happen to it after the scan, I could not have given them a confident answer.
The training had prepared me to use the technology, but not to support an informed conversation about it.
That distinction matters.
A clinician may operate a tool correctly while still feeling unprepared for the patient questions that influence transparency and trust.
When these gaps are overlooked:
patients may agree without being meaningfully informed
clinicians may use technology without feeling confident discussing it
education may increase awareness without changing practice
organisations may interpret poor uptake as resistance
strong products may struggle to earn trust and adoption
These are communication gaps, but their consequences can be clinical, operational and commercial.
Start where your audience is
The answer is not to remove the expertise.
It is to translate that expertise into something people can actually use.
For health and digital health organisations, this means designing communication around the audience’s starting point, not the expert’s finishing point.
Product education should go beyond features and operating instructions. It should prepare clinicians to understand a product’s role, limitations and implications, and answer the questions patients are likely to ask.
Patient information should not simply present accurate facts. It should provide enough context for people to understand what those facts mean for them.
And clinical education should do more than deliver information. It should help people apply that information in the reality of practice.
Sometimes a product is not being adopted because people do not understand where it fits.
Sometimes training is not changing practice because it assumes knowledge that is not there.
Sometimes patients are not taking the next step because the information answered the organisation’s questions rather than theirs.
Before creating more content, more education or more messaging, it is worth finding out where understanding is actually breaking down.
That is the part I am increasingly interested in: identifying why communication is not landing before deciding what needs to be created to fix it.
Because people do not always need more information.
Sometimes they need the missing piece that enables them to understand, trust and move forward.

Why “We Use AI” Isn’t Enough in Healthcare
Simply saying “we use AI” does not automatically create trust. This article explores why clear explanations, human oversight, patient communication and real-world workflow matter when introducing AI into healthcare.
AI is becoming increasingly visible across dentistry, oral health and healthcare.
Organisations are introducing AI-enabled tools into imaging, documentation, patient communication, workflow support and other parts of care delivery.
Many of these tools may offer real benefits.
But introducing AI creates another challenge too:
How do you explain it in a way that helps clinicians and patients understand what it actually does, where its boundaries are and why it is being used?
Because in healthcare, simply saying:
“We use AI.”
is not enough.
For some people, it sounds innovative.
For others, it raises immediate questions.
Is a machine making decisions about my care?
Who checks the output?
What happens if it gets something wrong?
Where does my data go?
Will this replace human judgement?
Those are not unreasonable questions.
And if organisations do not answer them clearly, uncertainty can quickly fill the gaps.
AI does not automatically create trust
AI is often communicated as though mentioning the technology itself demonstrates progress.
But healthcare is different from many other industries.
Novelty matters less than trust.
Patients may be interested in new technology, but they also want to understand how it affects them.
Clinicians may want to know how it fits into existing workflows, how reliable it is, where responsibility sits and when human judgement still needs to step in.
When those explanations are vague, heavily technical or overly promotional, communication can increase hesitation rather than reduce it.
The important questions are often fairly simple:
What does the AI actually do?
What does it not do?
Why is it being used?
Where does human oversight remain?
What happens if the system is uncertain?
How is patient information handled?
What problem is the technology actually solving?
Clear answers create context.
And in healthcare, context and boundaries are often what make new technology feel understandable rather than threatening.
There is a difference between using AI and explaining it well
Compare these two statements:
“This platform uses AI.”
and:
“This tool helps identify potential patterns for clinicians to review, while final clinical decisions remain with the healthcare professional.”
Both may describe technology involving AI.
But they communicate very different things.
The second gives the person reading it a clearer sense of the technology's role and, importantly, its limits.
That matters because successful implementation depends on more than whether a system technically works.
People also need to understand how it fits into the wider care pathway.
Who uses it?
At what point?
What does it influence?
What still requires human judgement?
What should happen when something does not go as expected?
If those questions have not been considered, the communication around the tool may not be ready for real-world implementation.
Patients are already asking questions about digital systems
I was reminded of this during a clinical appointment when a patient attended for a 3D scan that would later be sent to a laboratory.
Once I had explained the process, she asked:
“What happens to my data after the lab receives it? Do they keep a copy?”
It was a simple question, but an important one.
Her concern was not really about the scan itself.
She wanted to understand where her information was going, who would have access to it and what happened once it left the practice.
That interaction also highlighted something else.
Patients do not necessarily distinguish between digital scanning, cloud-based systems, laboratories, software platforms and AI-enabled technology.
From their perspective, their information may simply feel as though it is moving through a series of systems they cannot see.
As digital and AI-enabled workflows become more common, organisations may need to become far more intentional about explaining what happens behind the scenes.
Not because patients are necessarily anti-technology.
Because people naturally want clarity when their health information or care is involved.
Clinicians need language they can actually use
Technology companies often explain their products well at company level.
What is sometimes missing is the next stage:
How will the clinician, receptionist or wider dental team explain that technology to the patient?
In practice, clinicians often become the translators between technology and patients.
If they do not feel confident explaining:
what the tool does;
why it is being used;
where its limitations are;
when human judgement remains involved;
and how patient information is handled,
then implementation becomes much harder.
Not necessarily because the technology is poor.
Because uncertainty travels quickly.
This is why education, onboarding and patient-facing communication should not be treated as extras added after launch.
They are part of implementation.
Teams need explanations they can understand themselves and then confidently relay to somebody else.
If that translation is difficult, the communication has not travelled far enough.
Good AI communication starts with implementation thinking
The organisations that handle AI communication well are likely to think beyond the software itself.
They need to consider:
What will change in the workflow?
Who needs to understand the technology?
What will patients need to know?
Where might misunderstandings happen?
What concerns are likely to arise?
Where does human oversight sit?
What language will clinicians need when those questions come up?
That is where healthcare communication becomes part of implementation rather than simply part of marketing.
Because a technically impressive solution can still struggle if the people expected to use, explain or trust it do not understand how it fits into real life.
Clarity matters more as technology becomes more complex
As healthcare becomes more technologically advanced, communication does not become less important.
It becomes more important.
People are more likely to trust new technology when they understand what it is doing, why it is being used and where its boundaries are.
The strongest communication around AI is rarely the most futuristic.
It is often the clearest.
When people hesitate to use, trust or adopt a new technology, the answer is not always simply more content.
Sometimes the issue lies in what is being explained, where uncertainty enters the communication pathway, or how well the explanation fits the real clinical workflow.
That is exactly the kind of problem my Communication Clarity Audit is designed to explore.
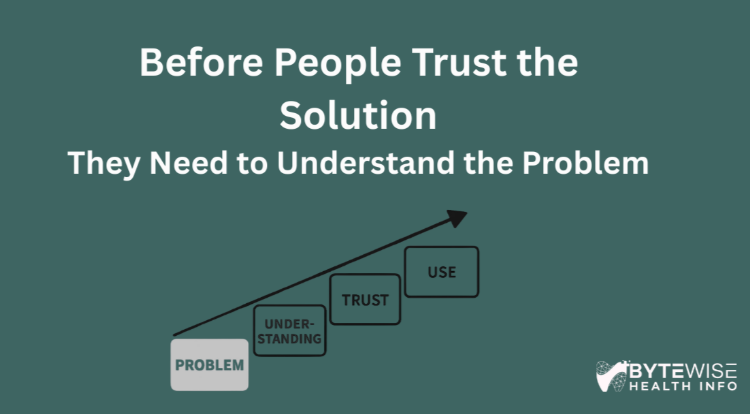
People Won’t Trust a Solution Until They Understand the Problem
Good healthcare solutions can struggle when people are shown the answer before they fully understand the problem. This article explores why problem clarity, workflow understanding and education are essential to trust, adoption and implementation.
There is no shortage of innovation across dentistry, oral health and digital health.
Organisations are developing products, platforms, services, educational programmes, AI-enabled tools and prevention initiatives designed to solve real problems for clinicians, teams and patients.
Many of those solutions are genuinely valuable.
But even a good solution can struggle if the audience has not first understood the problem.
And this is where healthcare communication can fall down.
Not because clinicians, practice owners or dental teams are resistant to change.
Often, they are already managing a great deal of it.
Clinical risk. Patient expectations. Team pressures. Regulatory responsibilities. Business demands. New technology. Time-poor working days.
So when an organisation leads with the product before clearly explaining the problem, the real-world relevance can get lost.
The message becomes:
“Here is what our solution does.”
But the person reading may still be thinking:
What problem is this actually solving?
Is this a problem in my setting?
Why does it matter?
What changes in the workflow?
What will my team need to understand?
What will my patients need to know?
That gap matters.
Because people do not usually trust a solution simply because it is innovative, evidence-based or technically impressive.
They trust it when they understand why it matters.
The missing step is problem clarity
This applies across oral health, digital health and clinical education.
A dental technology company may be introducing software or an AI-enabled tool.
An oral health brand may be explaining how a product fits into prevention or everyday care.
A CPD provider may be trying to change behaviour rather than simply deliver information.
A patient-facing campaign may share accurate advice but still fail to change what someone actually does.
The issue is not always the quality of the solution.
Sometimes, the missing step is problem clarity.
If people do not recognise the problem in their own world, the solution can feel like one more thing being added to an already crowded day.
Another tool.
Another platform.
Another training requirement.
Another piece of “innovation” asking for attention.
And when people are already stretched, another thing is rarely welcomed with a marching band and a packet of biscuits.
Education is part of implementation
This is why education often needs to come before selling.
Not instead of selling.
Before selling.
Because in healthcare, education is not just marketing support.
It is part of implementation.
When a new product, system or service enters a clinical setting, it rarely sits neatly in isolation.
It touches the team, the workflow, the patient conversation and often the trust relationship too.
Take something as apparently straightforward as an AI receptionist.
On paper, it might be described as improving efficiency, reducing telephone pressure or helping patients access care more easily.
All useful aims.
But in practice, the details matter.
If an AI receptionist places an emergency patient into the wrong type of appointment, the issue is not only technical.
It can affect clinical prioritisation, team workload, patient experience and trust.
So the important questions are not only:
“Does the tool work?”
They are also:
How does the practice understand what the tool is designed to do?
When should human judgement step in?
How are urgent situations recognised, escalated or checked?
How is the patient told what is happening?
What safeguards sit around the system?
If the product changes the patient journey, the explanation needs to be designed as part of the rollout, not added after confusion appears.
The ByteWise Problem-Clarity Test
Before asking people to buy, adopt or trust a solution, I think there are three useful questions to ask.
1. What problem does the audience need to recognise?
“Save time” and “improve efficiency” are used everywhere.
But they are often too vague to create meaningful understanding.
What does the problem actually look like in daily practice?
Phone overload?
Difficulty managing appointment demand?
Weak recall systems?
Inconsistent patient communication?
Poor uptake of preventive advice?
Team confusion around new guidance?
Patients not understanding why something matters?
The clearer the problem is, the easier it becomes for people to recognise it in their own setting.
And once they recognise the problem, the value of the solution becomes easier to understand.
2. What changes in the workflow?
This is the part that is often underestimated.
A product may look simple in a demonstration.
A resource may look clear in a PDF.
A CPD session may look effective on paper.
But implementation happens in a busy, interrupted, human environment.
Who uses it?
When do they use it?
What happens before and afterwards?
Who needs to explain it?
Who checks it?
What happens if something is misunderstood?
If the workflow is unclear, even a strong solution can become another thing for the team to manage.
3. What must people be able to explain?
This matters particularly in healthcare.
A practice owner may need to explain a new system to their team.
A clinician may need to explain a product, risk or referral to a patient.
A receptionist may need to explain why information is being collected.
A CPD provider may need to help a team understand not only what guidance says, but what they need to do differently afterwards.
If the person receiving the information cannot explain it clearly to someone else, the communication may not have travelled far enough.
And in healthcare, trust is often transferred through explanation.
From organisation to clinician.
From clinician to team.
From team to patient.
If that chain breaks, adoption becomes harder.
When good solutions look like more work
When the problem has not been made clear enough, good solutions can struggle for reasons that look like resistance but may actually be communication failure.
People may buy the product but not use it properly.
Teams may attend the training but not change behaviour.
Patients may receive the advice but not act on it.
Clinicians may understand the evidence but struggle to explain why it matters.
And organisations may conclude that the audience “didn’t get it”, when the explanation actually started too far ahead.
The audience was shown the solution before being helped to understand the problem.
That distinction matters.
Because adoption is not simply a sales outcome.
It is a behaviour-change process.
Behaviour rarely changes because the evidence is strong, the product is clever or the platform is impressive.
It changes when people understand the problem, trust the explanation and can see how the solution fits into real life.
Make the explanation part of the rollout
Better healthcare communication does not necessarily mean making communication longer.
It means making it more useful.
Instead of leading with:
“Look what our solution can do.”
It can be more effective to start with:
“Here is the problem your audience is already experiencing.”
“Here is why it matters.”
“Here is how it shows up in real life.”
“Here is what changes for the team, clinician or patient.”
“Here is what needs to be understood before this can be trusted and used.”
That is not dumbing the information down.
It is respecting the reality of the people expected to use, explain or act on it.
It is also commercially useful.
Because when people understand the problem clearly, they are better placed to recognise the value of the solution.
Before you ask for trust
Problem clarity before product claims.
Workflow understanding before implementation.
Patient trust before automation.
Education before selling.
Because if people do not understand the problem, they are unlikely to trust the solution.
And when a solution depends on real-world use, the explanation is not an afterthought.
It is part of the implementation.
Sometimes the answer is not more content.
Your communication may already be clinically accurate and professionally produced, but still be creating confusion, hesitation or poor adoption.
When that happens, the useful question is not simply, “What should we rewrite?”
It is:
Is communication contributing to the problem, where is the breakdown happening, and what needs to change first?
That is what my Communication Clarity Audit is designed to help uncover.

A Patient, a Missed Signal and a Bigger System Problem
Dental teams may be well placed to identify wider health risks, but screening alone is not enough. The real challenge is creating clear pathways so clinically useful information can move between professionals and lead to meaningful action.
A patient I had been seeing regularly suffered an aneurysm associated with previously undiagnosed high blood pressure.
It stayed with me.
Not because I thought dentistry should somehow have prevented what happened, but because it raised a bigger question:
If earlier signs had been picked up in another part of the healthcare system, would that information have had anywhere useful to go?
That question led me to think more closely about the role dental teams could play in wider health screening — and, more importantly, what needs to happen after a risk is identified.
Could dentistry play a wider role?
Dental professionals see many patients regularly, sometimes more consistently than other parts of the healthcare system.
We already take medical histories, assess general health risks and consider medical conditions when planning safe dental care.
That makes the dental setting an interesting place for wider health screening.
Blood pressure is a good example.
In England, blood-pressure screening is not yet a universal part of routine dental care, although NHS England has been trialling blood-pressure checks in dental and optometry settings as a way of identifying people at risk of cardiovascular disease.
In the United States, blood-pressure measurement is already recognised by the American Dental Association as an important screening vital sign within dental care.
So the idea itself is not particularly radical.
The more important question is what happens next.
Detection is only the beginning
Imagine a dental professional identifies a significantly raised blood-pressure reading.
The patient is advised to speak to their GP.
Then what?
In many situations, the patient becomes responsible for carrying that information from one part of the healthcare system to another.
Some will act immediately.
Others may delay.
Some may misunderstand the significance of what they have been told.
And some information may simply never reach the professional who needs to see it.
That is where the issue becomes much bigger than screening.
The problem is not simply whether we collect the data
Adding another check to a dental appointment has consequences.
It takes time.
It affects workflow.
It creates additional responsibility.
And clinicians will quite reasonably ask:
What happens to this information once I have collected it?
If identifying a raised blood-pressure reading leads to an effective referral pathway, appropriate follow-up and earlier intervention, the value is clear.
But if the process ends with:
“You should probably speak to your GP about that.”
then much of the burden still sits with the patient.
We may have generated useful information without creating an effective route for that information to influence care.
When information cannot travel
This is a wider healthcare communication problem.
Healthcare systems generate enormous amounts of information.
But information only becomes useful when it reaches the right person, at the right time, in a form that supports action.
A dental team can identify a potential risk.
A GP can manage hypertension.
A patient can act on advice.
But if those parts of the system are not connected, each person is working with only part of the picture.
That creates a communication and interoperability gap.
A workflow problem as much as a clinical one
It is tempting to frame questions like blood-pressure screening as:
Should dental teams do this?
But implementation requires a broader set of questions:
Who is responsible for acting on an abnormal result?
How should that information be communicated?
Is there a clear referral pathway?
Does the receiving professional know why the patient has been referred?
Can the dental team see whether follow-up happened?
How much additional work does the process create?
Where does responsibility begin and end?
Without those answers, adding more screening can create more data without necessarily improving the pathway around it.
We may have a connection problem
The real opportunity is not simply to collect more health information in dental settings.
It is to create better connections between the information already being collected across healthcare.
That means thinking about communication alongside technology.
How does information move?
Who needs it?
What context travels with it?
What happens next?
And how do we make sure the patient does not become the only bridge between two disconnected systems?
Those questions matter whether we are talking about blood pressure, diabetes risk, medications, oral cancer, or wider links between oral and systemic health.
Better detection needs better pathways
Screening has value when it changes what happens next.
That requires more than recognising a signal.
It requires clear communication, defined responsibility and systems that allow useful information to move between professionals.
Otherwise, we risk identifying more potential problems without building the pathways needed to respond to them.
The challenge is not simply detecting more.
It is making sure what we detect can actually lead somewhere.
This is the kind of systems and communication gap I help oral health and digital health teams explore — where useful information exists, but the pathway around it makes it harder to translate that information into real-world action.

When Symptoms Could Mean More: Why Information Alone Doesn’t Always Lead to Action
Digital health tools can provide clinically plausible information and still leave people unsure what it means or what to do next. This article explores how the way information is prioritised, connected and presented can influence real-world health decisions.
Oral symptoms are often treated in isolation.
Bleeding gums. Dry mouth. Bad breath.
But in practice, these signs do not always exist on their own. Sometimes they sit alongside wider symptoms such as tiredness, thirst or unexplained weight changes.
The challenge is that patients are rarely in a position to connect those dots themselves.
So I wanted to explore a simple question:
When someone uses a digital symptom checker, does the information help them understand what might matter — and what they should do next?
Looking beyond a local symptom
In clinic, I regularly hear patients say that they have had “no problems” before adding something like:
“Just a little bleeding.”
That response is understandable.
Bleeding gums can easily be normalised or dismissed as a local oral health issue. Sometimes improving oral hygiene may indeed be part of the answer.
But symptoms do not always sit neatly within one part of the body.
Persistent tiredness. Dry mouth. Increased thirst. Unexplained weight change.
Individually, these symptoms may appear unrelated. But when they occur alongside changes in oral health, they can sometimes contribute to a broader clinical picture.
The difficulty is not simply whether the information exists.
It is whether that information is surfaced in a way that helps someone understand the possible connections.
What happens when a patient looks for answers?
I tested Ada Health, a widely available symptom checker that asks users to enter symptoms before generating possible causes and general guidance.
I entered three symptoms:
bleeding gums
tiredness
dry mouth
The tool then asked a series of follow-up questions.
For this exercise, I deliberately kept the inputs relatively simple because I wanted to see how those initial symptoms were interpreted without adding further detail.
What the tool identified
The initial results included several plausible possibilities:
gingivitis
periodontitis
iron deficiency
menopause
Each result included further information about symptoms, risks, diagnosis, treatment, prevention and prognosis.
The information itself was useful.
What interested me more was how it was organised.
The possible explanations appeared largely as separate conditions, rather than as information that might help the user understand how different symptoms could relate to one another.
What was less visible
Diabetes did not appear prominently within the initial list of possible causes.
That does not mean the information was absent altogether. Diabetes was referenced later within supporting information about gingivitis as a potential risk factor.
The connection therefore existed.
But it was not surfaced at the point where it might most influence how a person interprets the combination of symptoms they are experiencing.
That distinction matters.
There is a difference between information being technically present and information being presented in a way that helps someone make sense of what they are seeing.
Where the communication gap appears
This is not simply a question of whether a digital tool contains the correct information.
It is also about:
what information is prioritised
how different pieces of information are connected
what the user is encouraged to pay attention to
which professional they are directed towards
how clearly the next step is explained
In this example, the results presented several clinically plausible possibilities, but gave less support for understanding how those possibilities might relate to each other.
The overall guidance also leaned towards general medical advice, even where dental assessment could clearly be relevant.
Although the gingivitis information explained that diagnosis would usually involve a dentist, that distinction was less prominent within the overall direction given to the user.
The information was there.
The pathway was less clear.
Why this matters
This reflects a wider communication challenge in digital health.
People rarely arrive with perfectly organised symptoms or enough clinical knowledge to understand how different signals might connect.
They notice something has changed.
They search for information.
They receive possible explanations.
And then they have to decide what those explanations mean and what to do next.
If the communication does not help them prioritise that information, important signals can become lost in a technically accurate list.
A patient may focus on one possible explanation while overlooking another.
They may not realise that oral health is relevant to the wider picture.
Or they may simply be unsure whether they should contact a dentist, GP, pharmacist or another service.
That uncertainty can influence whether someone seeks help, where they seek it, and how quickly they do so.
Information is only useful if people can act on it
Digital health tools have become increasingly sophisticated at recognising patterns and presenting possible explanations.
But identifying possibilities is only one part of effective health communication.
People also need help understanding:
what matters most
how different pieces of information relate
what level of concern is appropriate
where to seek help
what to do next
This is particularly important where oral health and wider health intersect.
The opportunity is not simply to add more information.
It is to design communication that makes existing information easier to interpret and act upon.
Because in healthcare, technically correct information is not always enough.
The way information is surfaced, prioritised and translated into guidance can shape real-world decisions.
And that is where communication design becomes part of the care pathway itself.
This is the kind of communication gap I help oral health and digital health teams identify — where the evidence is present, but the way it is presented makes it harder for people to understand what matters, what to do next, or how to act with confidence.

The Missing Layer in Dental Records: Biology
Dental records capture a huge amount of clinical information, but do they reflect the biological nature of disease? This article explores the gap between clinical understanding, structured data and the future of integrated oral healthcare.
We understand oral disease biologically — but we don’t always record it that way.
After more than 20 years in clinical practice, certain patterns become hard to ignore.
One of them sits quietly in the background of almost every patient interaction.
We now understand oral disease in far greater depth than we did even a decade ago. We talk about inflammation, biofilms, host response and systemic links as part of everyday care.
But when it comes to what we actually record, something doesn’t quite line up.
We’re treating disease as biological — but often documenting it in a way that remains largely mechanical.
There is a gap between how we understand disease and how we structure the information around it.
A biological understanding, a mechanical record
Dentistry increasingly recognises disease as a biological and inflammatory process.
Yet dental records still tend to centre on what we can see and measure: tooth surfaces, pocket depths, restorations, bleeding scores and treatment codes.
These are all essential.
Some, such as bleeding scores and changes in pocket depth, also give us valuable signals about inflammation.
But they are usually captured at specific moments in time.
What they do not always create is a clearly structured longitudinal picture of:
disease activity over time
patterns of inflammation
changing risk
how oral-health status interacts with wider health factors
Much of that understanding still sits within the clinician’s interpretation.
That judgement is informed and valuable, but it is not always captured in a way that can be easily followed, shared or analysed beyond that individual encounter.
What’s missing isn’t necessarily more data
The problem may not be a lack of information.
It may be that we need a different layer of information.
Clinicians already make nuanced judgements about disease activity, stability, progression and risk.
Periodontal staging and grading, bleeding patterns, maintenance history and changes in clinical findings all contribute to that picture.
But those insights can remain fragmented.
A clinician may understand that a patient with a history of advanced periodontal disease requires ongoing surveillance, for example, but that longitudinal understanding may not transfer cleanly if the patient changes provider or their information needs to move between systems.
The information exists.
The difficulty is turning it into something consistently structured and usable.
Why this matters beyond dentistry
This becomes particularly important when we think about how dentistry connects with the wider healthcare system.
If oral-health information is difficult to structure and interpret longitudinally, it becomes harder to:
connect oral and systemic health information meaningfully
share useful data across healthcare settings
identify patterns across populations
support risk-based and preventive approaches
make better use of emerging digital tools
Healthcare increasingly uses trends and trajectories, rather than isolated measurements alone, to understand risk and disease progression.
Dentistry has opportunities to do more of the same.
The challenge is not that clinical insight is absent.
It is that the way we record and structure that insight does not always make it easy to connect, analyse or use at scale.
Digital does not automatically mean transformed
Dentistry has made significant progress in digital adoption.
Electronic dental records are standard in many settings. AI-supported tools are emerging. Diagnostic technologies continue to evolve.
But digitising a system does not automatically change what the system is designed to capture.
In some cases, we have taken an existing model of care and made it digital.
That can make information more efficient, legible and accessible, while leaving the underlying structure largely unchanged.
So while the technology may be evolving quickly, the way we define and organise clinically meaningful information may evolve more slowly.
That distinction matters.
Where change is emerging
There are already signs of movement.
Developments in salivary diagnostics, biofilm analysis, AI-supported assessment and risk-based care are creating opportunities to understand oral disease in more dynamic ways.
These technologies may allow us to focus not only on what has already happened, but also on what is happening now and what may happen next.
But capability alone is not enough.
If new biological information cannot be incorporated meaningfully into records, workflows and wider health systems, much of its potential value may remain isolated.
The technology and the information architecture have to evolve together.
A shift in what we consider meaningful
The bigger question, then, may be less about collecting more information and more about deciding what deserves to be structured as meaningful clinical data.
For a long time, dentistry has understandably focused on findings and interventions:
what we see, what we measure and what we do.
But if disease is dynamic and patient-specific, there is value in capturing patterns too.
Not just individual measurements, but trajectories.
Not simply whether disease is present, but how activity changes.
Not only which treatment has been delivered, but how risk develops over time.
That is as much a conceptual shift as a technological one.
It means moving from documenting events towards representing processes.
The gap isn’t knowledge — it’s translation
Dentistry does not lack clinical understanding.
We already recognise relationships between oral health, inflammation, risk and wider health.
The difficulty is translating that knowledge into information that can be consistently structured, shared and interpreted beyond the individual clinician.
That makes this more than a data problem.
It is also a communication problem.
What information do we prioritise?
How do we represent complex clinical judgement?
How do we make that information meaningful to another clinician, another system, or potentially another part of healthcare entirely?
These questions will become increasingly important as dentistry becomes more connected with wider digital-health systems.
If dentistry is to play a more integrated role in healthcare, it is not enough simply for systems to connect.
The information within those systems also has to make sense.
And that starts much earlier than interoperability itself.
It begins with what we choose to capture, how we structure it and what we decide is clinically meaningful.

The Adoption Gap
Why do good digital health tools sometimes fail to become part of everyday practice? This piece explores the gap between what works in theory and what fits into real clinical workflows — and the role communication, habit and friction can play in adoption.
Why good digital health tools don’t always get used
A new tool gets introduced into practice.
It’s evidence-based. It makes sense.
People are shown how to use it. A few give it a go.
And then, gradually, it fades into the background.
Not because it doesn’t work.
But because it never quite fits into real life.
What we assume
We often assume that if something works, people will use it.
That adoption is simply a matter of awareness, training, or time.
But in practice, it rarely works that way.
It’s something I’ve seen play out more than once — a new system introduced with good intentions, but without fully understanding how it fits into day-to-day practice.
What actually happens
Adoption isn’t a feature of the tool.
It’s a feature of the system around it.
The workflows it lands in. The time available. The priorities already competing for attention.
And the small, often invisible frictions that shape what actually gets used day to day.
I’ve started to think of this as the adoption gap — the space between something working in theory and it being used in real life.
Where things break down
In many cases, the problem isn’t the tool itself.
It’s how — or whether — it fits into real-world practice.
Sometimes it adds a few extra steps to an already full workflow: more clicks, more decisions, a little more time.
Sometimes it isn’t clear when it should be used, or how it fits alongside existing processes.
Sometimes the value is there, but it isn’t immediately visible at the moment decisions are being made.
And often, there is no space for it to become a habit.
No reinforcement. No integration.
Just another well-intentioned tool sitting slightly outside the flow of everyday care.
These gaps often sit somewhere between how something is designed, how it is communicated, and how it is expected to be used in practice.
Why this matters
When something doesn’t get used, it is easy to assume the problem is the tool.
That it needs improving, refining or replacing.
But sometimes the bigger issue sits elsewhere.
It sits in the gap between what works in theory and what fits into real life.
That gap can be easy to overlook, but it quietly shapes whether a tool succeeds, stalls or disappears into the background.
A better question to ask
When a digital health tool isn’t being used, the most useful question may not be:
What’s wrong with the tool?
It may be:
What is getting in the way of people understanding where it fits, why it matters and how to use it within the realities of everyday practice?
Adoption problems often sit in that space between design, communication and real-world behaviour.
And that is where some of the most useful answers can be found.

The Toothbrush Missing From Hospital Care
A patient’s hospital stay prompted a bigger question: what happens when oral hygiene is overlooked during admission? This piece explores hospital oral care, pneumonia risk, and the communication gaps that can stop useful evidence from becoming everyday practice.
A small clinical moment, and a bigger question about prevention in healthcare
Sometimes it’s the smallest clinical encounters that make you pause.
A patient I saw recently apologised to me for the state of her mouth.
She had just come out of a long stay in hospital and told me she hadn’t even had a toothbrush.
She looked embarrassed, as if she’d somehow failed.
But the moment stayed with me for a different reason.
It reminded me how easily oral care can disappear from the picture when someone is unwell, admitted to hospital, dependent on others, or simply trying to get through the day.
When oral care falls off the radar
When someone is in hospital, oral care can quickly become a low priority.
Patients may be too unwell, too exhausted, or physically unable to manage it themselves. Understandably, clinical teams are focused on stabilising illness, monitoring medications and managing more immediate risks.
But the mouth doesn’t pause just because someone is in hospital.
Dental plaque continues to build, bacteria continue to grow and the oral environment can deteriorate surprisingly quickly.
That matters for more than comfort.
The overlooked pneumonia risk
Oral health can play a role in hospital outcomes.
Bacteria from dental plaque can be aspirated into the lungs and contribute to hospital-acquired pneumonia.
Importantly, this is not limited to ventilated patients. Non-ventilator hospital-acquired pneumonia (NV-HAP) affects patients who are not mechanically ventilated and represents a significant patient-safety problem.
There is also evidence that relatively simple preventive measures may make a difference. A 2023 systematic review and meta-analysis of randomised trials found that daily toothbrushing was associated with a reduction in hospital-acquired pneumonia among hospitalised patients.
It is a striking example of how something that looks small and routine can have wider clinical significance.
The mouth is still too often treated separately
Despite growing awareness of oral-systemic health, the mouth is still frequently treated as if it sits outside the rest of healthcare.
Oral care can be viewed primarily as a hygiene or comfort measure rather than something that may contribute to broader clinical outcomes.
But biology does not recognise professional or organisational boundaries.
Microorganisms in the mouth can move beyond it. A patient’s oral health can interact with their wider health. And information that sits in one part of the healthcare system may be highly relevant somewhere else.
That raises a wider question.
How much useful clinical information is being missed simply because healthcare is still organised in separate silos?
A communication and systems problem
My patient did not develop pneumonia during her hospital stay, and her previously good oral health meant the short period of reduced care did not lead to lasting problems.
But the encounter made me think about the wider system.
The evidence connecting oral health with general health is not necessarily the missing piece. In many cases, we already have useful information.
The harder problem is making sure that information reaches the right person, in the right form, at the point where someone can act on it.
That may mean clearer clinical guidance.
It may mean better integration of oral health information into wider medical records.
It may mean designing digital systems that make relevant risks easier to spot rather than leaving clinicians to join the dots themselves.
The technology matters, but so does the communication around it. A piece of evidence can be clinically important and still have very little impact if it remains buried in a paper, trapped within one profession, or poorly translated into everyday practice.
Sometimes prevention is not about discovering something new.
It is about making better use of what we already know.
And sometimes a missing toothbrush reveals a much bigger gap in the system.
References
Ehrenzeller S, Klompas M. Toothbrushing and prevention of hospital-acquired pneumonia: systematic review and meta-analysis. 2023.
Patient Safety Authority. Hospital-Acquired Pneumonia in Pennsylvania: Non-ventilated versus Ventilated Patients. Pennsylvania Patient Safety Authority.

Are We Developing — or Just Documenting?
In healthcare, are we genuinely developing through CPD — or simply documenting that we’ve done it? This article explores how better reflection and clearer learning goals can turn professional development into meaningful change in practice.
Why healthcare CPD and personal development plans need to focus on practice change, not just completion.
A newly qualified colleague said something to me recently that stayed with me.
“What’s the point in doing a personal development plan properly? I’ll just do it at the end.”
She was half-joking, but she was also being honest.
In many healthcare roles, we’re expected to maintain a personal development plan, complete continuing professional development, and document our learning across a multi-year cycle.
So leaving it all until the end is tempting.
But it also raises a bigger question.
Are we genuinely developing — or are we simply getting better at documenting development?
Being “on track” isn’t the same as developing
At around the same time, I’d been reviewing my own PDP and checking whether I was on track with the learning goals I’d set.
But I realised I was focusing more on whether I had completed what I said I would do than on whether anything had actually changed.
I was measuring activity.
Not development.
And I suspect that is quite easy to do.
Most healthcare regulators and professional bodies are understandably clear about what needs to be recorded. We are expected to log learning, connect it to our role or professional outcomes, and include some form of reflection.
Those requirements matter. They support professional standards, accountability and public trust.
But being clear about what needs to be documented does not necessarily mean we are clear about what meaningful development looks like in practice.
Why activity doesn’t always become improvement
Healthcare professionals are usually very good at recording activity.
Courses attended. Webinars completed. Articles read. Hours logged.
What is harder is working out whether that activity has changed anything.
Has it made us more confident?
Changed the way we make decisions?
Improved the way we respond in difficult situations?
Reduced risk?
Changed how we communicate with patients or colleagues?
Professional development matters because learning should eventually show up somewhere in practice.
If it doesn’t, then CPD can become little more than evidence that something was completed.
What a PDP is actually for
A personal development plan should be more than a form.
At its best, it is a thinking tool.
It gives us a reason to step away from the day-to-day and ask questions such as:
Where do I hesitate?
Where do I feel stretched?
What situations do I find difficult repeatedly?
What would make my work safer, clearer or easier?
What kind of professional do I want to become?
That is very different from simply asking:
“What course should I do next?”
A meaningful development plan is not really a list of learning activities.
It is a decision about direction.
Why PDPs can lose their value
One of the problems is that many healthcare professionals are told to create a PDP, link CPD to it and reflect on their learning, without ever being properly shown what useful reflection looks like.
So the PDP can gradually become another administrative requirement.
Something we complete because we have to.
Not something we actively use.
And that is understandable.
When clinical workloads are high and time is limited, it is far easier to record what we have done than to stop and think deeply about whether it has changed our practice.
Systems tend to reward completion because completion is easy to measure.
Reflection is harder.
Behaviour change is harder still.
Turning reflection into something practical
One way to make a PDP more useful is to start with practice rather than courses.
Pick:
one thing that regularly slows you down,
one situation that carries genuine risk, and
one area where you still do not feel fully confident.
Then work backwards.
What knowledge, skill or support would make a difference?
What could you learn?
What could you practise?
What would you want to notice changing afterwards?
That creates a much clearer connection between learning and real-world practice.
When systems reward completion over thinking
Over the years, in clinical practice and in education-focused work, I’ve seen how easily professional development can drift into routine.
Not because healthcare professionals lack motivation.
But because busy systems often make completion easier than reflection.
If the process mainly asks whether something has been documented, people will naturally optimise for documentation.
That is not necessarily a problem with the individual.
It can also be a problem with the way the system has been designed.
And that matters, because better professional development does not necessarily require more training or more paperwork.
Sometimes it requires better prompts, clearer guidance and more support for reflection.
What better support could look like
I’m increasingly interested in how professional learning systems can help clinicians connect learning with real decisions in practice.
Not by adding more boxes to complete.
But by making it easier to think about:
what needs to change,
why it matters,
what learning would genuinely help, and
how we would recognise improvement afterwards.
Because when reflection is supported properly, professional development becomes much more than evidence for a portfolio.
It becomes part of safer, more confident practice.
Clarity turns learning into safer practice.
Why “Clinically Proven” Isn’t Enough — And What Actually Builds Trust in Health Products
Clinically proven’ sounds reassuring — but it often isn’t enough to build trust or drive real-world use. Here’s why strong evidence alone doesn’t guarantee adoption, and what actually makes health products easier to understand, recommend, and use.
Over the past few months, I’ve noticed how often health products lean on the phrase “clinically proven.”
It sounds reassuring. It feels scientific. It ticks a box.
But increasingly, it isn’t doing the job brands think it is.
The Real Problem
Most health brands aren’t trying to mislead anyone.
They invest in formulation.
They commission research.
They follow regulatory guidance.
The science is often solid.
And yet… adoption is slower than expected.
Clinicians hesitate.
The people using the product day to day feel unsure.
Not because the product doesn’t work — but because trust hasn’t quite landed.
This is where many strong products start to lose momentum.
Why “Clinically Proven” Isn’t Enough
From a clinician’s perspective, “clinically proven” is only the starting point.
If I’m going to recommend something to a patient, I need two things:
To be confident that solid research has actually been done
A clear, simple explanation I can pass on in plain English
If I can’t quickly understand it myself, I can’t confidently explain it to someone sitting in my chair.
And if I’m not confident… I won’t recommend it.
What Happens in Real Life
I see this all the time in practice.
Patients come in confused by claims, ingredients, and competing messages — especially around toothpaste, electric toothbrushes, and newer oral health technologies.
They’ll say things like:
“I saw this online… is it actually any good?”
“There are so many options — I don’t know what to choose.”
So they turn to clinicians as their trusted source.
But here’s the key:
If clinicians don’t feel equipped to explain a product clearly, it often stays on the shelf.
Not because it’s ineffective.
But because it’s poorly communicated.
A Practical Lens for Evaluating Product Messaging
When reviewing health product content, I often come back to three simple questions:
Can a clinician quickly understand the evidence?
Can they explain it to a patient in 30 seconds?
Does it sound honest, balanced, and realistic?
If the answer to any of these is “no,” trust weakens.
The Trust–Information Paradox
There’s an interesting paradox in healthcare communication.
Too little information confuses people.
Too much information overwhelms them.
And in both cases, trust drops — leading to the same outcome:
No action.
No recommendation.
No purchase.
No traction.
Good products quietly stall.
What Builds Real Trust in Health Products
The strongest health brands don’t rely on slogans alone.
They:
show their evidence clearly
explain what it does — and what it doesn’t mean
respect clinicians’ time
respect the intelligence of the people using the product
They make it easy for professionals to feel confident passing the message on.
And that’s what builds real trust.
Bringing It Together
If this feels familiar, the issue is rarely the product itself.
It’s how the evidence is being translated, understood, and used in practice.
When communication is clear, clinically grounded, and relevant to real-world use, adoption becomes much easier.
What to Do Next
If you’re working on a health product and want to understand where trust may be breaking down, I’ve created a practical framework to help you assess and improve your messaging:
👉 5 Things Trusted Oral Health Brands Get Right
You can also explore why strong digital health products often struggle with adoption in practice:
👉 5 Reasons Your Digital Health Product Isn’t Being Used

What Dental Records Could Reveal About Cognitive Health — and Why Health Systems Need to Talk to Each Other
Dentistry sees patients regularly over many years, creating a unique record of behaviour, self-care, and subtle health changes. What could dental records reveal about cognitive health if health systems were better connected?
Healthcare systems often treat dental records and medical records as separate worlds. Yet dentistry sees patients regularly over many years, creating a unique longitudinal view of behaviour, self-care, and subtle health changes.
That continuity means dental teams sometimes notice early shifts in routine, memory, or self-care long before those changes are recognised elsewhere in the healthcare system.
The question isn’t whether dentistry can diagnose cognitive decline. It can’t.
But could observations captured in dental records contribute to earlier, more connected care if health systems were better integrated?
Mrs Chen’s Story
Mrs Chen has been coming to the same dental practice for eight years.
Always punctual. Always prepared. Chatting easily with the front desk staff.
Then last month, she arrived confused about her appointment time.
This month, she forgot her bank card for the first time and seemed unusually flustered during her routine cleaning.
Her dental hygienist notices these changes.
But her GP never sees this information.

Mrs Chen isn’t alone.
Many people living with early cognitive change show up regularly somewhere long before symptoms are recognised — not in neurology clinics, not in memory services, but in the dental chair.
Dentistry Runs on Cadence
Adults in England average around four to five GP consultations each year according to analysis of English primary care records, but many of these interactions are brief, problem-focused appointments. Increasingly, they are conducted remotely, or patients may see a different clinician each time depending on availability.
Dental care operates differently.
Patients often return even when nothing feels wrong — for routine examinations, hygiene visits, or ongoing periodontal care. These appointments are typically face-to-face and often involve the same dental professionals over many years.
That rhythm creates something powerful: continuity.
Dental teams come to understand a patient’s usual behaviour, communication style, and level of self-care. Over time, that familiarity makes subtle shifts easier to notice.
Not as diagnosis.
Not as prediction.
But as small signals that something in a person’s health story may be changing.
This Isn’t About Prediction — It’s About Connection
This isn’t a dementia piece. It’s a systems piece.
Research continues to explore links between gum disease, inflammation, and cognitive health. But the real focus here is simpler: observations that remain trapped inside dental records.
Instead, the question is what happens when small, relevant observations in dentistry stay isolated within separate systems — and what might change if those observations were safely, consentedly connected to the wider health picture.
Oral health and cognitive health share many of the same underlying pressures: ageing, diabetes, cardiovascular disease, smoking, medication burden, depression, frailty, nutrition, sleep, and social inequality.
Research increasingly shows these connections are not coincidental — they are systemic.
People don’t live these as separate categories. They live them as one life.
So the more useful question may not be “does gum disease predict dementia?”
It may simply be this:
If oral health reflects the same underlying health pressures shaping cognitive health, what could dental observations contribute to earlier, more connected care?

When health records stay separated, patterns stay invisible.
Dentistry sees patients regularly over many years, creating a unique record of behaviour and self-care. When those observations remain trapped in isolated systems, important signals can be lost.
The Shared Landscape of Risk
Oral health and cognitive health share many of the same risk factors:
• ageing
• diabetes
• cardiovascular disease
• smoking
• medication burden
• depression
• frailty
• nutrition and sleep
• social and economic inequality
These aren’t separate categories in real life.
People live them as one health story.
So the question becomes:
If oral health reflects the same pressures shaping wider health, what could dental observations contribute to earlier, joined-up care?
The Overlooked Asset: Time
Dentistry sees people over time.
A patient’s “normal” becomes visible — and so does its drift.
Consider a few everyday scenarios.
Case 1
A retired teacher who has managed complex periodontal care independently for years suddenly struggles to follow post-treatment instructions and misses follow-up appointments.
Case 2
A businessman known for meticulous oral hygiene begins attending with noticeably poorer dental care, explaining he has simply “been busy”.
Case 3
A grandmother who always brings photos of her grandchildren becomes quieter, more anxious during procedures, and less socially engaged.
None of these examples are dramatic.
They’re small inconsistencies — changes that don’t fit the patient’s usual baseline.
And that raises a difficult question:
What should clinicians do with observations that feel meaningful but not diagnostic?
Right now, those signals often stay inside the dental record.
The Informatics Gap
Dentistry’s continuity offers something valuable: longitudinal observation.
But that visibility is stranded inside separate systems.
A dental note about memory lapses may never meet a GP’s concern about medication adherence.
A hygienist’s observation about declining self-care may never connect with wider health changes.
The signals exist.
But the infrastructure doesn’t allow them to form patterns.
If healthcare systems want earlier support for patients, the bottleneck may not be new biomarkers.
It may simply be better connectivity between the records we already have.
What Shared Health Records Could Enable
Imagine if dental observations could travel — not as diagnostic claims, but as structured, consent-based summaries.
For example:
“Patient history: 8 years of consistent routine care, punctual and well-prepared. Recent changes include two missed appointments in three months after years of consistency. Patient appeared more forgetful during recent visits and required additional support with post-care instructions.”
Shared carefully and with patient consent, observations like this could support several quiet shifts in care.
Continuity of concern
Medical teams could see patterns rather than isolated events.
Earlier feedback loops
Changes in oral health or behaviour might prompt earlier conversations.
Reduced burden on families
Patients wouldn’t need to repeat the same information across multiple systems.
True collaboration between teams
Dental and medical clinicians could see the same evolving picture.
Learning From Connected Data
Integrated health records would not simply improve communication.
They would also support learning.
Linked data could help reveal:
• how behavioural signals cluster with frailty or medication complexity
• how oral health changes evolve alongside wider health pressures
• which early interventions actually help patients maintain independence longer
Not to predict outcomes.
But to design care that fits real lives better.
Why This Still Isn’t Normal
Despite the potential, integrated dental and medical records remain rare.
Several barriers persist.
Separate systems and standards
Dental and medical IT infrastructures evolved independently.
Workflow pressure
Clinicians cannot manage more alerts. They need smart summaries that fit existing workflows.
Cultural separation
Dentistry is still often treated as separate from mainstream healthcare, and its data follows the same path.
The challenge of disconnected health records is explored further in my white paper on integrated dental and medical records.
Privacy Must Come First
Any system connecting dental and medical records must be built on strong privacy foundations.
This means:
• granular patient consent
• transparent information sharing processes
• the ability to withdraw consent easily
• clear professional boundaries around observational information
Trust is not just technical.
It’s about giving people control over their own health story.
A Quieter Kind of Progress
Healthcare innovation often focuses on dramatic breakthroughs.
But sometimes progress is quieter.
Dentistry already observes change.
It already documents behaviour, continuity, and subtle shifts over time.
The opportunity lies in allowing those observations — when appropriate and with consent — to travel across healthcare systems.
Not as predictions.
Not as diagnoses.
But as context that helps care become more connected.
No new test.
No dramatic technology.
Just better communication between the records we already keep.
And that may be one of the most meaningful improvements healthcare systems could make.
About the Author
Colette Lawler is a UK-based dental clinician and medical writer specialising in oral health, digital health, and evidence-based healthcare communication.
With more than 20 years of clinical experience and a background in oral health science and health informatics, she helps healthcare organisations, health technology teams, and oral health brands translate complex evidence into clear, trustworthy communication that supports better decisions.
She is the founder of ByteWise Health Info, where she focuses on the intersection of oral health, digital health systems, and integrated healthcare communication.
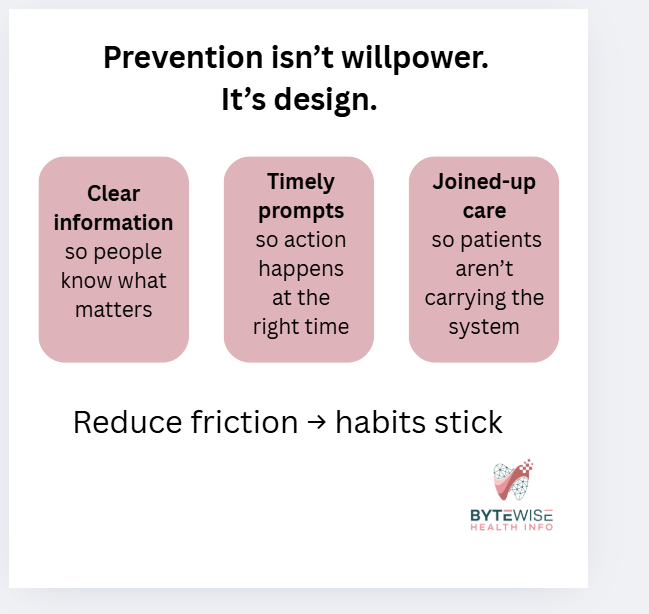
Why health advice doesn’t stick — and what oral health can teach us about making habits easier
Health advice doesn’t fail because people don’t care. It fails because real life creates friction. Here’s what oral health can teach us about designing habits that actually stick — with clearer priorities, better prompts, and more supportive systems.
January is peak “new habits” season.
And yet, every year, many of those habits quietly fade — not because people don’t care, but because real life gets in the way.
In oral health, I see this all the time.
I’m Colette — a UK-based dental clinician and medical writer — and I spend a lot of time thinking about the overlap between oral health, prevention, and the systems (and tech) that make healthy habits easier to stick to.
Because advice can be clinically spot-on… and still not stick.
In clinic, it’s often clear that knowledge isn’t the missing piece. Many patients already know the basics: brush twice a day, clean between teeth, watch the sugar.
And yet, a patient said to me recently:
“I know what I’m meant to do… I just don’t manage it.”
That gap — between knowing and doing — is where prevention often breaks down.
And it’s why motivation alone is rarely the answer.
Why health advice doesn’t stick (even when it’s correct)
Most oral health (and general health) advice is well-intentioned and evidence-based.
But behaviour doesn’t happen in ideal conditions. It happens on busy mornings, late nights, shift patterns, school runs, sensory overload days, anxious days, and the “I’ve got nothing left in the tank” days.
So when habits slip, it’s rarely because someone doesn’t care.
More often, it’s because the habit sits behind too much friction.
Common reasons health habits fail (the friction points)
Too much complexity
Too many products, too many claims, too many “rules”. When people feel confused, they often do nothing.
No clear priority
If everything sounds equally important, it’s hard to know what matters today.
Timing
Advice is often given at a moment when people can’t act. The moment passes, and life takes over.
Shame and self-judgement
If someone feels they’ve already “failed”, they avoid the topic altogether. Shame doesn’t build habits — it blocks them.
Life factors that don’t get acknowledged
Neurodivergence, anxiety, depression, medication-related dry mouth, chronic illness, caring responsibilities, cost. These aren’t edge cases — they’re real life.
This is why I keep coming back to a simple idea:
Prevention is easier when the system is designed to support it — not with more pressure, but with better support.
Knowing vs doing: where prevention really lives
Most prevention challenges sit in the gap between:
Capability — Do I know how? Do I have the tools?
Opportunity — Is my environment set up to help me?
Motivation — Do I want to do this, and does it feel worth it?
We often focus heavily on motivation: try harder, be consistent.
But opportunity is frequently the missing piece — the prompts, routines, environment, and joined-up care that make follow-through more likely.
This is also where digital tools can help — including reminders, smart prompts, and in some cases wearables — as long as they’re designed around real human behaviour, not perfect routines.
What better systems (and tech) could do
This isn’t about fancy gadgets or downloading yet another app that gets abandoned by Thursday.
It’s about reducing friction and making prevention easier to repeat.
1. Personalised prevention, not one-size-fits-all
Oral health advice is often generic — but people aren’t.
Someone with dry mouth, braces, diabetes risk, previous gum disease, or high sugar exposure needs different support from someone who’s low risk.
Better systems could translate risk into clear, usable guidance like:
“Here are your top two priorities this month.”
“Here’s the one habit that will give you the biggest win.”
“Here’s what to focus on until your next visit.”
Clarity reduces overwhelm.
2. Prompts at the right moment (not random reminders)
Most reminders fail because they arrive when you can’t act.
More effective prompts show up at the point of decision — when a routine is already happening.
Even low-tech prompts work well:
linking interdental cleaning to an existing habit
keeping brushes or floss where you actually sit
a simple routine card on the bathroom mirror
recall messages sent during opening hours, when booking is easy
Tech can help with timing — but the goal is simple: make the next right action easier.
3. Joined-up records that support joined-up care
Oral health is linked to systemic health, medication, pregnancy, and chronic conditions — yet records are often siloed. This is something I explore further in my white paper on integrating dental and medical health records.
When data isn’t joined up, we rely on:
patients repeating their story
memory (not a safe clinical tool)
missed prevention opportunities
Better integration could flag:
diabetes risk and gum inflammation
medication-related dry mouth
anticoagulants and dental planning
osteoporosis medications
pregnancy-related inflammatory windows
This isn’t about “more data”.
It’s about the system doing some of the heavy lifting — so patients don’t have to.
4. Prevention that continues between appointments
Most people see a dental professional occasionally — but habits are daily.
Systems and tech could help bridge that gap with:
simple check-ins
consistent, non-judgemental encouragement
short, personalised “next step” nudges
easy access to the right education at the right time
Prevention works best when it feels supported, not like a once-a-year reset.
Three tiny friction-reducers to try this week
You don’t need a personality transplant. You need a simpler setup.
1. Put tools where the habit actually happens
Out of sight = out of routine. Move tools to where you intend to use them and leave them on show.
2. Attach the habit to something you already do
Borrow an existing routine so you don’t rely on memory.
3. Shrink the task
A “minimum version” still counts. Consistency beats perfection.
A quick note on shame
If you’ve ever felt embarrassed about your oral health routine, you’re not alone.
But shame doesn’t create good habits.
It creates avoidance.
Better systems support people — they don’t judge them.
Where I’m going with this in 2026
This year I’m leaning further into the systems side of prevention.
Not just what we tell people to do — but what actually helps people do it, consistently, in real life.
That includes:
clearer risk communication
better-timed prompts
joined-up records
and tech that supports habits without adding guilt
I’m also starting a behaviour change course to strengthen this side of my work — so my content is not only clinically accurate, but genuinely usable.
One last question
What’s the biggest thing that gets in the way of oral health habits sticking — for you, or for your patients?
Forgetfulness?
Time?
Anxiety or sensory issues?
Cost or access?
Medication or health factors?
Or just… life?
These real-world barriers are where better prevention design starts.

The Ultimate Guide to Choosing the Right Toothpaste
Choosing toothpaste shouldn’t feel overwhelming. This simple guide breaks down fluoride, hydroxyapatite, whitening pastes and SLS free options so you can choose the right toothpaste with confidence.
Choosing a toothpaste should be simple.
But walk down any supermarket aisle and it can suddenly feel like you need a degree in chemistry to understand what you are looking at.
"Whitening." "Enamel repair." "Nature identical minerals." "Ultra micro nano crystal technology."
The claims can be confusing, even when you do understand the science.
This guide breaks down the key toothpaste ingredients, what they actually do, and how to choose the best toothpaste for your needs in clear, normal human language.

The toothpaste aisle, decoded. A simple guide to ingredients and what they do.
How to Understand a Toothpaste Label
Fluoride – the essential one
Fluoride is the ingredient with the strongest, longest standing evidence for preventing tooth decay.
It helps to:
strengthen enamel
slow early decay
make teeth more resilient
This is why fluoride toothpaste is recommended for most adults.
You will usually see fluoride shown as ppm (parts per million). This simply describes the concentration of fluoride in the toothpaste.
Types of fluoride you will see
Most toothpastes use one of two main forms:
Sodium fluoride
Stannous fluoride
Both protect against decay.
Stannous fluoride also offers added benefits for gum health and sensitivity relief, which can make it a good choice for people with bleeding gums or sensitive teeth.
For everyday use, adults should choose toothpaste with 1,350 to 1,500 ppm fluoride.
How Much Fluoride Do Children Need?
For children, the recommended fluoride level and the amount of toothpaste used depends on their age:
Under 3 years: a smear of toothpaste with at least 1,000 ppm fluoride
Ages 3 to 6: a pea sized amount of 1,000 to 1,500 ppm
Age 7 and above: usually fine to use adult strength toothpaste (1,350 to 1,500 ppm)
Children often prefer milder flavours. It is absolutely fine to stay with a child friendly toothpaste as long as the fluoride level is appropriate.
When my three were younger, we often had several different tubes lined up on the bathroom shelf. One for each age and stage.
If your bathroom looks similar, you are not doing anything wrong. It is just a phase, and once everyone moves onto adult toothpaste, things get slightly simpler.
A note on how much toothpaste to use
Young children swallow toothpaste more often, and their adult teeth are still developing under the gums.
Using the right amount helps prevent fluorosis (a harmless but sometimes mottled appearance on enamel).
Under 3 years: a smear
Ages 3 to 6: a pea sized amount
A pea sized amount also makes it safe for children aged 3 and over to use adult strength toothpaste if needed, especially if they are more prone to decay.
If a child is at higher risk of tooth decay, your dentist or hygienist may recommend stronger fluoride toothpaste sooner, or prescribe a paste that is not available over the counter.
Hydroxyapatite toothpaste: what it does (and what to look for)
Hydroxyapatite is the mineral your enamel is made from, which is why it’s showing up in toothpaste. It’s a biomimetic (“nature-mimicking”) ingredient that supports enamel—often chosen by people who want a fluoride-free toothpaste. It isn’t a like-for-like replacement for fluoride, but it has its own role.
How hydroxyapatite works
Hydroxyapatite can help to:
“fill in” tiny surface defects on the enamel
reduce sensitivity
smooth the tooth surface
support remineralisation
For people looking for fluoride-free toothpaste, hydroxyapatite is one of the few ingredients with emerging evidence behind it.
Some toothpastes even combine fluoride and hydroxyapatite for a dual approach.
There is no standardised “ideal concentration” for hydroxyapatite yet. Brands are not always required to list the percentage. Some formulas use around 10 per cent, others vary.
Instead of focusing on a number, focus on:
choosing a reputable brand
checking that hydroxyapatite appears reasonably high on the ingredient list
Top tip:
If you spot words like “biomimetic”, “microcrystalline” or “nature identical mineral” on the packaging, it is often a marketing-friendly way of describing hydroxyapatite.
A Quick Note on Ingredient Sensitivities (Including During Chemotherapy)
Some people react to certain toothpaste ingredients.
Not with tooth sensitivity, but with irritation of the mouth tissues.
One of the most common triggers is SLS (sodium lauryl sulphate), a foaming agent found in many toothpastes.
SLS is considered safe, but for some people it can:
trigger mouth ulcers
cause a stinging or burning feeling
irritate the cheeks or lips
make the mouth feel drier
People undergoing chemotherapy can be especially sensitive to foaming agents and stronger flavours, because treatment often leaves the mouth dry, delicate, or more prone to ulceration.
If you notice toothpaste making your mouth feel sore, or if you are going through chemotherapy, switching to an SLS free, mild flavour toothpaste can make brushing far more comfortable.
Most brands clearly label “SLS free” on the front of the packaging.
If not, a quick check of the ingredient list on the back will tell you. You are looking for “Sodium Lauryl Sulphate” (or “Sodium Lauryl Sulfate” with the American spelling).
If it is not listed, the toothpaste is generally SLS free.
SLS free toothpastes clean just as effectively. They simply foam less.
Whitening Toothpaste – What Actually Works?
You have probably seen the promises:
“Instant whitening.”
“Five shades brighter.”
Some claims are hopeful. Some are pure sparkle. So what do whitening toothpastes actually do?
Mild abrasives – the stain polishers
Most whitening toothpastes use ingredients like hydrated silica to gently polish away surface stains from coffee, tea and red wine.
These are great for lifting daily staining, but they will not change the natural colour of your teeth.
Chemical lighteners – the gentle lifters
Some formulas contain low dose hydrogen peroxide or carbamide peroxide.
These can brighten the surface slightly, but they do not reach deeper pigments in the same way professional whitening gels do.
Optical brighteners – the illusionists
Some pastes use blue pigments (such as blue covarine) that temporarily change the way light reflects off enamel, giving an instant but short lived brightness boost.
What I see in practice
In day to day practice, the best “everyday brightening” results usually come from:
a mildly abrasive whitening toothpaste
used with an electric toothbrush
It will not transform your tooth shade, but it can noticeably lift surface staining.
A note on tooth sensitivity
Whitening toothpastes can increase tooth sensitivity, especially if they are more abrasive.
If your teeth tend to twinge:
try a whitening plus sensitivity toothpaste, or
alternate your whitening paste with a regular fluoride toothpaste
The Bottom Line – How to Choose the Right Toothpaste
Here is a quick summary to help you choose:
For cavity protection:
A fluoride toothpaste with 1,350 to 1,500 ppm fluorideFor sensitivity:
Toothpaste with stannous fluoride or potassium nitrateFor a more “natural” option:
Hydroxyapatite toothpaste from a reputable brandFor gum health:
Stannous fluoride or CPC (cetylpyridinium chloride)For whitening:
Mild abrasive whitening paste for stain removal
Peroxide toothpastes for gentle brightening
(Professional whitening for bigger shade changes)For ingredient sensitivities or frequent ulcers:
SLS free toothpasteDuring chemotherapy or if your mouth feels sore and delicate:
SLS free, mild flavour toothpaste and a soft brush
If you are ever unsure what is right for your mouth, speaking to a dental professional is the safest place to start.
About the Author
Colette Lawler is a UK based dental hygienist and therapist and freelance medical writer. She specialises in oral health, oral cancer awareness, and digital health communication, with a focus on turning complex science into clear, practical advice.

Welcome to ByteWise: Where Oral Health, Digital Health and Human Stories Meet
ByteWise is here — a space where oral health, digital health and human stories meet. In this first post, I share why the mouth matters more than people realise, how it connects to whole-body health, and what you can expect from the ByteWise community moving forward.
I’m so glad you’re here.
If we haven’t crossed paths properly yet, I’m Colette — a dental clinician turned medical writer who’s spent more than twenty years watching how the mouth quietly reflects what’s happening elsewhere in the body. Sometimes long before anyone thinks to connect the dots.
When I’m not in clinic or writing, I’m juggling three kids, a husband on brutal shifts, and a sprocker who’s made off with more shoes than I care to admit. Real life is beautifully chaotic… and if I’m honest, it sparks half my ideas.
Because through all of it, one thing has stayed constant: curiosity.
Curiosity about patterns, early clues, and the quiet ways oral health mirrors whole-body health.
ByteWise has been brewing for a while, and this blog — alongside my newsletter — is my way of bringing that curiosity to life. Think of it as a place where we explore how the mouth, the body and technology are far more connected than most people realise.
Why Start ByteWise Now?
Because oral health is still treated like a side mission in the bigger health conversation.
And it shouldn’t be.
Your mouth reacts to hormones.
It mirrors inflammation.
It often changes before the rest of your body sends clearer signals.
Yet despite all this, oral health is almost entirely missing from digital-health tools — even though it’s one of the most powerful early indicators we have.
ByteWise exists to help change that: gently, clearly, and with a bit of personality along the way.
If you’re curious about how oral health fits into the bigger picture — hormones, chronic disease, AI, digital tools and everything in between — you’ll feel right at home here.
What You Can Expect from ByteWise
🧠 Insightful, research-backed micro deep dives
Exploring the fascinating, often-overlooked ways the mouth connects with the rest of the body.
📘 Smart, digestible explainers
Clear, human explanations without the jargon overload.
🩺 Real clinical stories & honest reflections
Two decades in the treatment room have taught me a lot about people, patterns and the power of early detection.
💡 Digital tools worth knowing about
Wearables, apps, AI, emerging salivary tech — the tools that genuinely support health, not overwhelm it.
✨ Practical, everyday insights
Small things you can look for that make a real difference to comfort, confidence and whole-body health.
Why This Matters
The mouth is still the missing data layer in so many areas of healthcare — women’s health, cardiovascular disease, diabetes, mental health.
And now, with AI, biomarkers and smart sensors evolving rapidly, we’re entering a new era of connected health.
But technology is only useful if people understand it.
That’s where clear, human communication comes in — and that’s what ByteWise is here to offer.
Who This Blog Is For
Clinicians, writers, founders, women’s-health advocates, digital-health thinkers — and anyone who simply wants to understand their body a little better.
If you’re curious, this space will feel like home.
A Quick Promise from Me
Everything you find here will be:
Clear
Warm
Evidence-based
Grounded in real clinical experience
Free from hype, gimmicks and unnecessary drama
Written with the same honesty and care I bring to my clinical work.
Coming Up Next: Inside Your Toothpaste
The next post takes you behind the scenes of toothpaste ingredients — what actually protects your teeth, what doesn’t, and why the formula matters more than the flavour.
Thank you for being here.
Let’s grow this ByteWise community together.
Colette x