


A Patient, a Missed Signal and a Bigger System Problem
Dental teams may be well placed to identify wider health risks, but screening alone is not enough. The real challenge is creating clear pathways so clinically useful information can move between professionals and lead to meaningful action.
A patient I had been seeing regularly suffered an aneurysm associated with previously undiagnosed high blood pressure.
It stayed with me.
Not because I thought dentistry should somehow have prevented what happened, but because it raised a bigger question:
If earlier signs had been picked up in another part of the healthcare system, would that information have had anywhere useful to go?
That question led me to think more closely about the role dental teams could play in wider health screening — and, more importantly, what needs to happen after a risk is identified.
Could dentistry play a wider role?
Dental professionals see many patients regularly, sometimes more consistently than other parts of the healthcare system.
We already take medical histories, assess general health risks and consider medical conditions when planning safe dental care.
That makes the dental setting an interesting place for wider health screening.
Blood pressure is a good example.
In England, blood-pressure screening is not yet a universal part of routine dental care, although NHS England has been trialling blood-pressure checks in dental and optometry settings as a way of identifying people at risk of cardiovascular disease.
In the United States, blood-pressure measurement is already recognised by the American Dental Association as an important screening vital sign within dental care.
So the idea itself is not particularly radical.
The more important question is what happens next.
Detection is only the beginning
Imagine a dental professional identifies a significantly raised blood-pressure reading.
The patient is advised to speak to their GP.
Then what?
In many situations, the patient becomes responsible for carrying that information from one part of the healthcare system to another.
Some will act immediately.
Others may delay.
Some may misunderstand the significance of what they have been told.
And some information may simply never reach the professional who needs to see it.
That is where the issue becomes much bigger than screening.
The problem is not simply whether we collect the data
Adding another check to a dental appointment has consequences.
It takes time.
It affects workflow.
It creates additional responsibility.
And clinicians will quite reasonably ask:
What happens to this information once I have collected it?
If identifying a raised blood-pressure reading leads to an effective referral pathway, appropriate follow-up and earlier intervention, the value is clear.
But if the process ends with:
“You should probably speak to your GP about that.”
then much of the burden still sits with the patient.
We may have generated useful information without creating an effective route for that information to influence care.
When information cannot travel
This is a wider healthcare communication problem.
Healthcare systems generate enormous amounts of information.
But information only becomes useful when it reaches the right person, at the right time, in a form that supports action.
A dental team can identify a potential risk.
A GP can manage hypertension.
A patient can act on advice.
But if those parts of the system are not connected, each person is working with only part of the picture.
That creates a communication and interoperability gap.
A workflow problem as much as a clinical one
It is tempting to frame questions like blood-pressure screening as:
Should dental teams do this?
But implementation requires a broader set of questions:
Who is responsible for acting on an abnormal result?
How should that information be communicated?
Is there a clear referral pathway?
Does the receiving professional know why the patient has been referred?
Can the dental team see whether follow-up happened?
How much additional work does the process create?
Where does responsibility begin and end?
Without those answers, adding more screening can create more data without necessarily improving the pathway around it.
We may have a connection problem
The real opportunity is not simply to collect more health information in dental settings.
It is to create better connections between the information already being collected across healthcare.
That means thinking about communication alongside technology.
How does information move?
Who needs it?
What context travels with it?
What happens next?
And how do we make sure the patient does not become the only bridge between two disconnected systems?
Those questions matter whether we are talking about blood pressure, diabetes risk, medications, oral cancer, or wider links between oral and systemic health.
Better detection needs better pathways
Screening has value when it changes what happens next.
That requires more than recognising a signal.
It requires clear communication, defined responsibility and systems that allow useful information to move between professionals.
Otherwise, we risk identifying more potential problems without building the pathways needed to respond to them.
The challenge is not simply detecting more.
It is making sure what we detect can actually lead somewhere.
This is the kind of systems and communication gap I help oral health and digital health teams explore — where useful information exists, but the pathway around it makes it harder to translate that information into real-world action.
Why “Clinically Proven” Isn’t Enough — And What Actually Builds Trust in Health Products
Clinically proven’ sounds reassuring — but it often isn’t enough to build trust or drive real-world use. Here’s why strong evidence alone doesn’t guarantee adoption, and what actually makes health products easier to understand, recommend, and use.
Over the past few months, I’ve noticed how often health products lean on the phrase “clinically proven.”
It sounds reassuring. It feels scientific. It ticks a box.
But increasingly, it isn’t doing the job brands think it is.
The Real Problem
Most health brands aren’t trying to mislead anyone.
They invest in formulation.
They commission research.
They follow regulatory guidance.
The science is often solid.
And yet… adoption is slower than expected.
Clinicians hesitate.
The people using the product day to day feel unsure.
Not because the product doesn’t work — but because trust hasn’t quite landed.
This is where many strong products start to lose momentum.
Why “Clinically Proven” Isn’t Enough
From a clinician’s perspective, “clinically proven” is only the starting point.
If I’m going to recommend something to a patient, I need two things:
To be confident that solid research has actually been done
A clear, simple explanation I can pass on in plain English
If I can’t quickly understand it myself, I can’t confidently explain it to someone sitting in my chair.
And if I’m not confident… I won’t recommend it.
What Happens in Real Life
I see this all the time in practice.
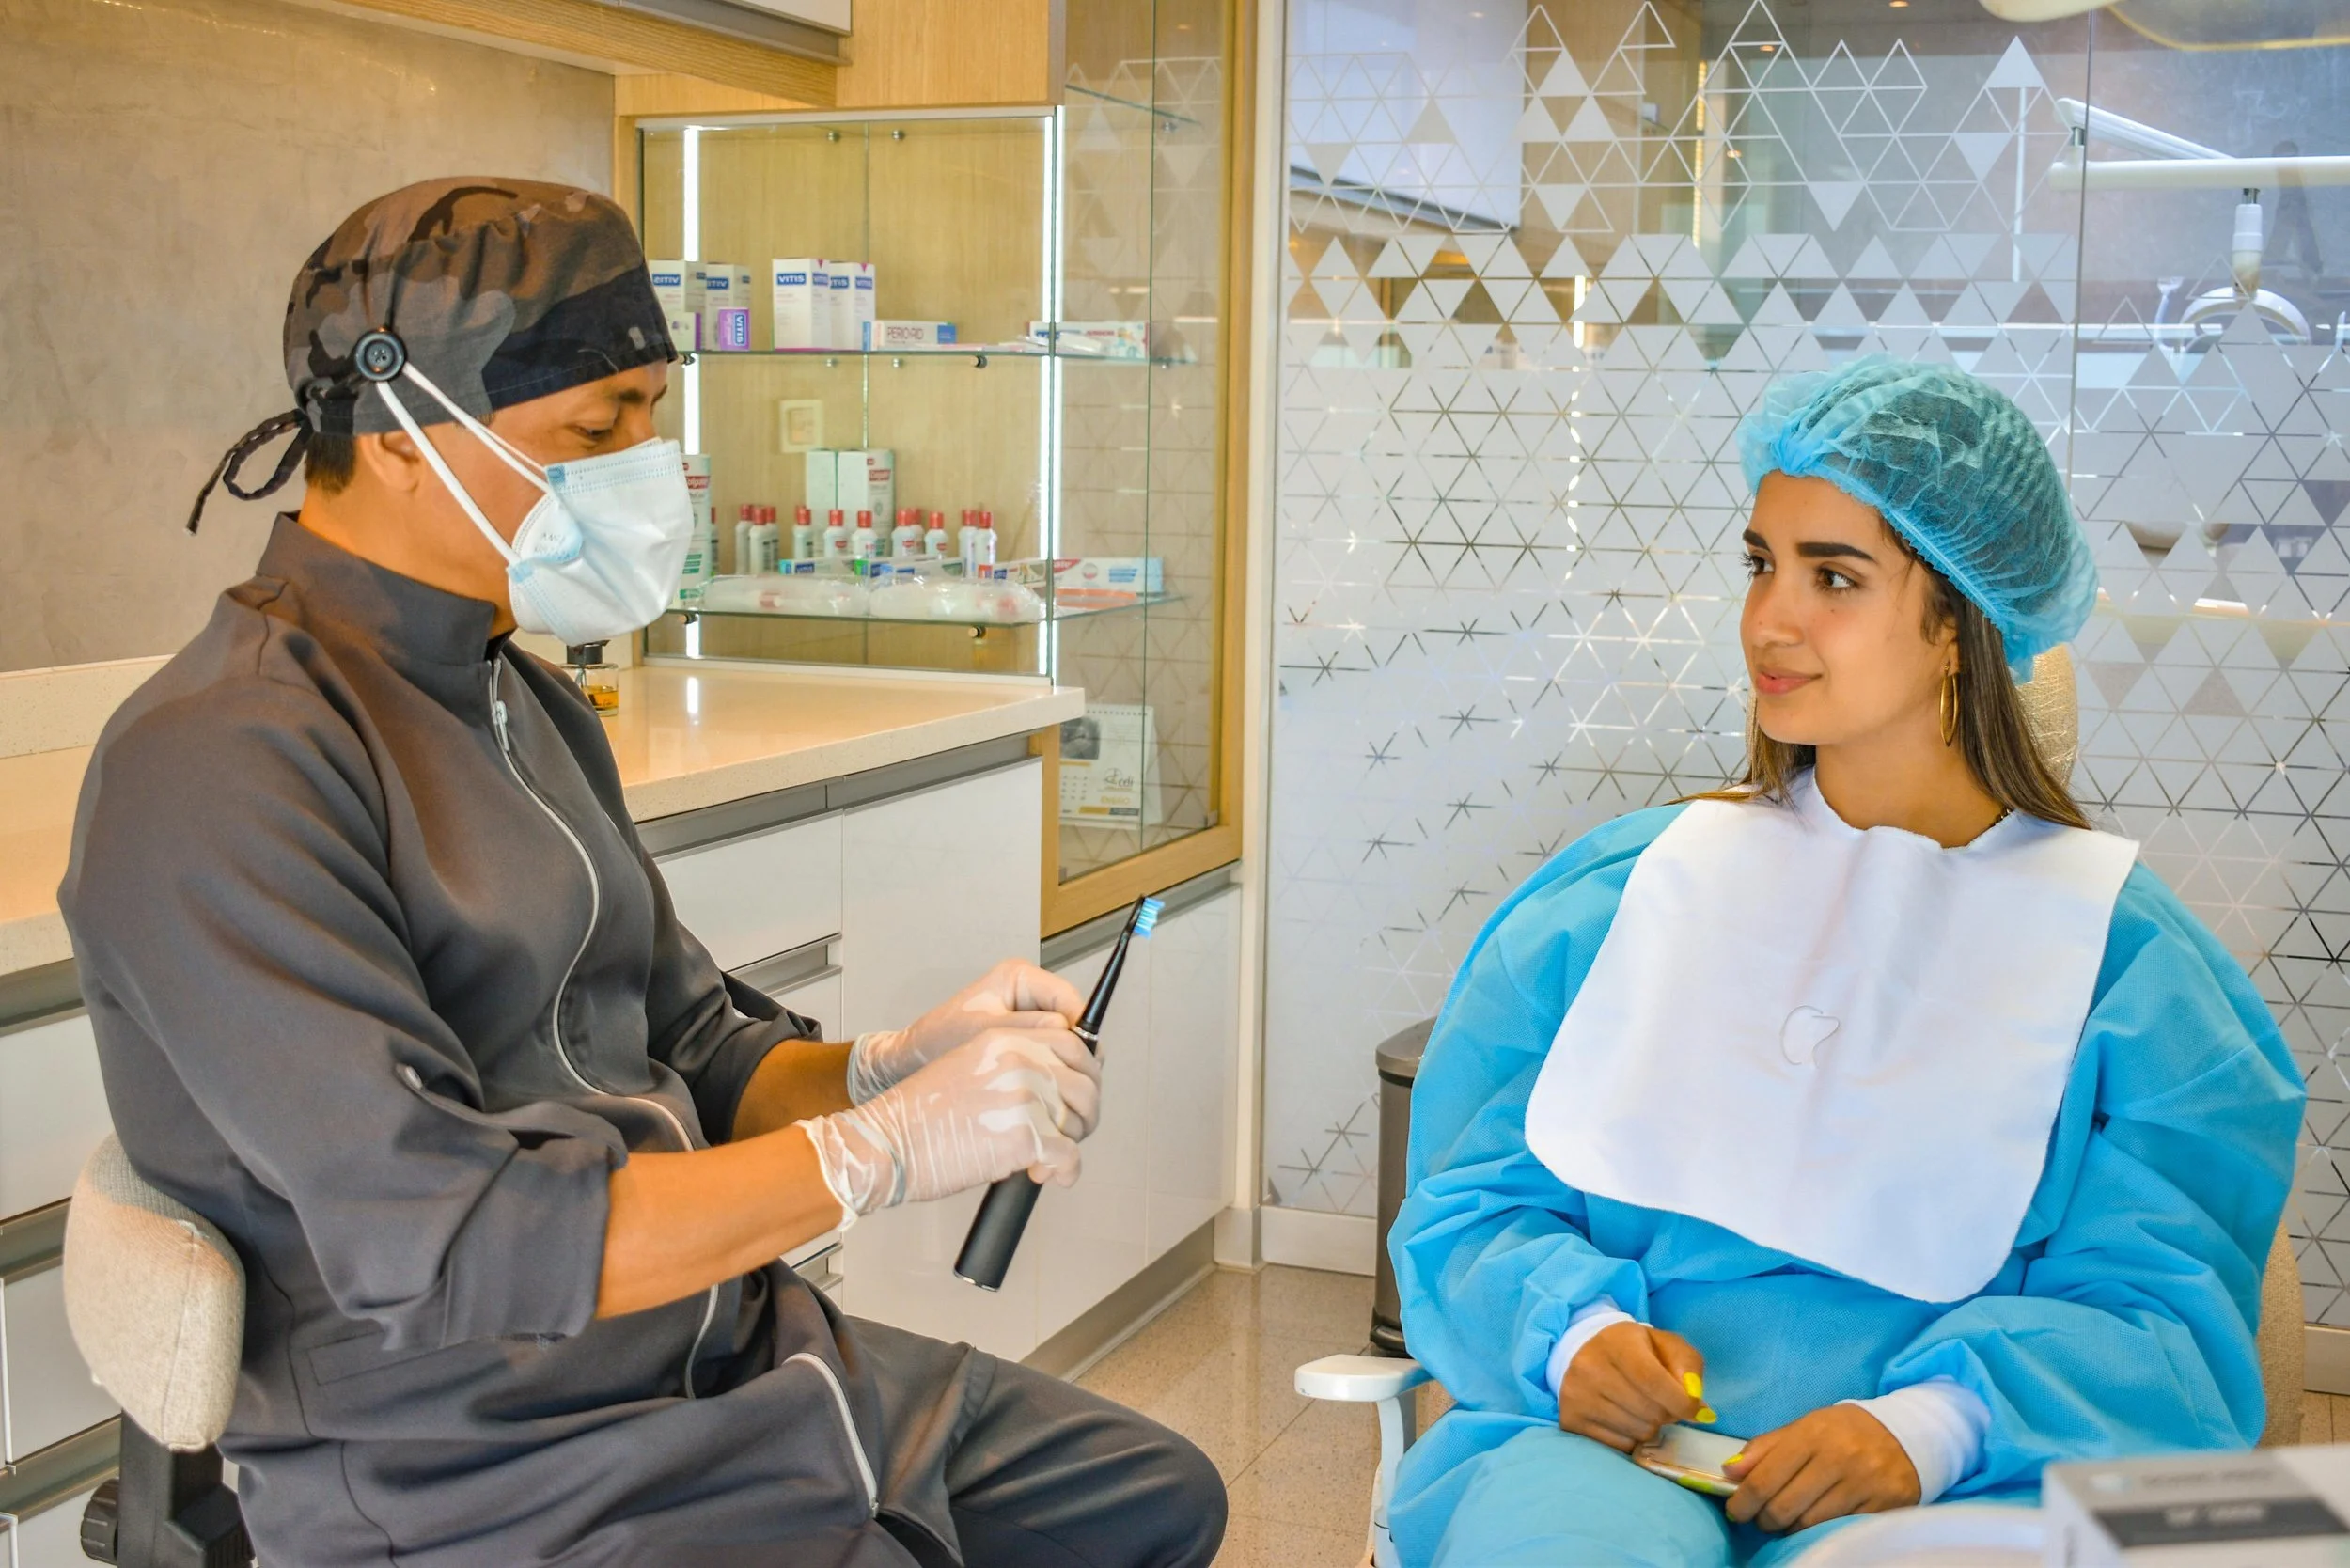
Patients come in confused by claims, ingredients, and competing messages — especially around toothpaste, electric toothbrushes, and newer oral health technologies.
They’ll say things like:
“I saw this online… is it actually any good?”
“There are so many options — I don’t know what to choose.”
So they turn to clinicians as their trusted source.
But here’s the key:
If clinicians don’t feel equipped to explain a product clearly, it often stays on the shelf.
Not because it’s ineffective.
But because it’s poorly communicated.
A Practical Lens for Evaluating Product Messaging
When reviewing health product content, I often come back to three simple questions:
Can a clinician quickly understand the evidence?
Can they explain it to a patient in 30 seconds?
Does it sound honest, balanced, and realistic?
If the answer to any of these is “no,” trust weakens.
The Trust–Information Paradox
There’s an interesting paradox in healthcare communication.
Too little information confuses people.
Too much information overwhelms them.
And in both cases, trust drops — leading to the same outcome:
No action.
No recommendation.
No purchase.
No traction.
Good products quietly stall.
What Builds Real Trust in Health Products
The strongest health brands don’t rely on slogans alone.
They:
show their evidence clearly
explain what it does — and what it doesn’t mean
respect clinicians’ time
respect the intelligence of the people using the product
They make it easy for professionals to feel confident passing the message on.
And that’s what builds real trust.
Bringing It Together
If this feels familiar, the issue is rarely the product itself.
It’s how the evidence is being translated, understood, and used in practice.
When communication is clear, clinically grounded, and relevant to real-world use, adoption becomes much easier.
What to Do Next
If you’re working on a health product and want to understand where trust may be breaking down, I’ve created a practical framework to help you assess and improve your messaging:
👉 5 Things Trusted Oral Health Brands Get Right
You can also explore why strong digital health products often struggle with adoption in practice:
👉 5 Reasons Your Digital Health Product Isn’t Being Used